Tuesday, May 21, 2013

Help Wanted

We've already noted that carriers seem to be actively avoiding the Exchanges due to go online in the next few months. Of course, that's for the individual market - the small group market must be doing gangbusters, though, right?

Right?

Turns out, maybe not:

"The California Health Benefit Exchange has put out a call for general agents ...  to recruit, train, supervise and support the retail agents that help the small employers that sign up for the state's Small Business Health Options Program (SHOP) exchange plans."

But why should they?

All along, agents have been told, at least implicitly, that their services aren't necessary (cf: Navigators). Agents must undergo fairly extensive scrutiny and training, and must continually update their professional education. All of which comes at a cost, in time and in money. Of course, the folks in Sacramento understand the value of the agent in the process, and are willing to pay for the very best.

No, I didn't think you'd fall for it:

"Exchange managers want general agents to keep estimates for total costs under $3 million"

Really, and just how many groups do they think will sign up?

Small Businesses are Exempt from PPACA?

A couple of weeks ago The Hill reported that 48% of small business owners believe that PPACA will hurt their business. In the article there is a quote from President Obama about the impact this will have on small business. He said: "Some small businesses are being told their costs are going to go up, even though they're exempted from the law" or stand to benefit from it.

I am a small business owner working within a large insurance agency. I have two employees and I provide benefits including medical insurance. Under our arrangement I currently pay 100% of the premiums. I have been able to do so because we are a healthy low risk and because my employees understand the value of the benefit and know that it is part of the overall compensation package.

I strongly object to the notion that I am exempted from the law. It is true I can drop coverage and not pay a penalty. But that would put my employees into exchanges where every dollar they have to spend in premiums is more than what they currently pay. My key employee, based on family income, wouldn't qualify for a subsidy. She (52) and her spouse (53/smoker) would be looking at a $15,000 pay cut. For this key employee I currently pay around $8,700 a year. Even if I gave her a raise by that amount it still costs her a ton of money out of pocket.

We will also see our premiums go up. Our insurance company has informed us that because of community rating we are looking at an increase of 50% or more. On top of this factor we also will pay a PCORI fee, a reinsurance fee, a risk adjustment fee, and a market share fee. In total these fees will represent roughly a 3% increase. Add to that we now must provide an array of additional benefits without limitations that we don't use nor need. Last, they will also charge us more because our industry code is a low risk one.  In total my guess is the costs will rise by close to 75%.

My premium increases are going to make it unaffordable to remain in business and dropping coverage simply shifts an enormous burden onto the people who help the business be successful. So, my question to President Obama and HHS is please explain how my business stands to benefit from PPACA?

Dumber and Dumberer

As the Exchange Countdown Clock slowly - inexorably - winds down, our attention turns to the eternal question: "what's next?"

Ostensibly, folks who plan on buying their new health insurance from one of the public Exchanges will turn to one of those new-fangled "Navigators" for help. After all, these folks are new to the insurance purchasing process, and need highly trained folks brimming with integrity and advanced insurance knowledge.

Or maybe not:

"At a private briefing with federal officials last month, committee aides say they were told there would be no criminal background checks for navigators or requirements that they hold a high-school diploma"

Contrast this to actual licensed insurance agents. Here in Ohio (and I imagine these requirements are fairly universal across the other 57 states) one must have (at least) a high school diploma (or equivalent), take 40 hours of pre-licensing training, pass a rigorous licensing exam with a minimum of 70% correct answer, and complete over 20 hours of Continuing Education every two years.

Now who would you trust with your financial and personal information, let alone to help guide you to an informed purchasing decision?

Yeah, thought so.

PCIP Could Save the World

or at least the US Private Insurance system. It is an old rule of thumb that 20% of your population accounts for 80% of your claims. Hospitals account for 50% of all spending and most of the excessive cost and profit.

PCIP found this out when they blew through their allotted 5 billion to quickly. Being from the Government and always looking to help they had a very effective solution;

http://www.lifehealthpro.com/2013/05/17/feds-post-pcip-regs

"The federal PCIP program run by the U.S. Department of Health and Human Services (HHS) will set most reimbursement levels at just 100 percent of the Medicare reimbursement rates, officials said"

For doctors this might be a slight haircut but for large hospitals, the ones racking up large bills, used to getting 300-400% of Medicare, or more, this will be noticeable.

If the Government was truly interested in being useful they would provide catastrophic insurance to reign in hospital spending and leave all the day to day care and the other 80% of the population alone. This would immediately make insurance affordable for the majority of the country which would likewise drop the percentage uninsured. It would also do so without all the other intrusive programs and requirements of the ACA.    

Monday, May 20, 2013

The ObamaTax Dodge

As employers quickly realize that the ObamaTax will not, in fact, be lowering premiums by 3000%, they (and their agents) have begun looking for ways to minimize the impact.

Contrary to popular belief, new ObamaTax plans don't actually have to be all that benefits-rich. In fact, the Feds themselves agree that a plan which covers basically just the Minimum Essential Benefits "would appear to qualify as acceptable minimum coverage under the law, and let most employers avoid an across-the-workforce $2,000-per-worker penalty for firms that offer nothing."

That is, an employer could drop his existing full-coverage (or Catastrophic, for that matter) plan in favor of one of these "bare bones" configurations (Bob, you were way ahead of your time!). Coupled with a supplemental plan to cover some days in the hospital and the like, and the landscape suddenly changes.

This may prove especially attractive for employers with low-wage employees, who want to avoid the ObamaTax employer mandate penalty but can't afford to offer full-blown coverage. And if the premiums are low enough, perhaps those subsidies will cover the lion's share of their premiums.

Interesting concept.

JeffLinks Tuesday

FoIB Jeff M sends along two very helpful ObamaTax items.

First, courtesy of the Kaiser Foundation, a helpful (and free!) ObamaSubsidy calculator. This will no doubt help take some of the edge off those massive premiums hikes looming on the horizon.

But probably not.

Second, if you're a business owner, heads' up. Ms Shecantbeserious has released  a handy little FAQ sheet with timely (right) info on the SHOP (Small Business Health Options Program).

'Course, that presupposes that these things will ever actually get off the ground.

You can download the FAQ here.

Stupid Carrier Trick - Logging edition

Recently, I sold and delivered a policy to a client who, when applying, chose the monthly draft ("check-o-matic") premium payment option. This is a convenient way to budget premiums and, at least with this company, the second least expensive way to do so (typically, carriers impose a surcharge depending on how often premiums are paid - monthly, quarterly, etc). When the policy was approved and we had set an appointment for delivery, he indicated that he'd decided to change to annual pay.

Not a major issue - I notified our general agent (GA) for that carrier, and an amendment form was included with the policy. So far, no big deal. When I delivered the policy, I had the client sign that form (along with approximately 273 others) and sent it back in the handy, pre-paid envelope.

So far, so good.

You can imagine my surprise, then, to receive an email from the GA that "the new, re-issued policy" was on the way.

What new, re-issued policy?

Turns out, this carrier - even though we had signed and returned the amendment form - has decided that it needs to re-issue the entire policy, and over the weekend I received another half pound of paper (really!). Sent to me for a mere $2.50 of USPS postage.

I am far from a "tree-hugger," but even I find this offensive. Nothing substantive changed in the policy - why wouldn't the carrier simply print up and send out a little "certificate" noting the change?

Sheesh!

Saturday, May 18, 2013

Rate Kaboom!

We've been warning about this for quite some time: if you think health insurance rates are bad now, just wait until the ObamaTax is in full swing.

But what do we know, anyway? Remember our Dear Leader promised rates would plummet by 3000%.

Turns out, not so much:

"Internal cost estimates from 17 of the nation's largest insurance companies indicate that health insurance premiums will grow an average of 100 percent under Obamacare, and that some will soar more than 400 percent"

Math sure is hard.

[Hat Tip: FoIB Jeff M]

Friday, May 17, 2013

HSA's still on life support

At the risk of mangling metaphors, the water's still murky and the jury's still out on the fate of Health Savings Accounts [ed: "mangled?!" How 'bout strangled?]. I've contended for a while (most recently here) that, due to the "cost-sharing reduction" requirements which essentially outlaw true High Deductible Health Plans, HSA's are DOA.

In fairness, Bob disagrees (agreeably, of course); he's "becoming more convinced there is a viable market for major med (and ancillary lines) outside the exchange. Yes, the products will still need to provide EHB's and adhere to MLR ... but they will also have more flexibility."

But we're both speaking in generalities here; that is, about the marketplace as a whole. LifeHealthPro's Allison Bell has an interesting article today on a specific segment of the market: those who may be eligible for tax subsidies:

"Low-income people will still be able to use health savings accounts (HSAs) after Jan. 1, 2014 ... For low-income people who want to use HSAs, the problem is that getting help with paying deductibles could make it impossible for a "qualified health plan" ... An individual who would not be eligible for the tax advantages of an HSA because the plan variation to which he or she would be assigned does not qualify as a [high-deductible health plan] may purchase the plan without cost-sharing reductions," officials said"

Well how nice for them. But what about those of us in the middle class, who aren't going to be eligible for subsidies? I asked Allison if this proclamation applied to us, as well, and she kindly replied:

"I think the guidance here is just about low/moderate income people who are getting cost-sharing subsidies that would make having an HSA and getting exchange coverage mathematically impossible. I think regular folks could still have an HSA and a non-subsidized, non-cost-sharing-subsidized plan, because the deductible could still be high enough that the plan would be compatible with the HSA rules."

Can't fault her for honest reporting, but I'm still unconvinced. After all, the whole "skin in the game" nature of HSA plans is in direct - and stark - contrast to plans that have to include all manner of pre-defined benefits payable at 100% (such as birth control convenience items).

If the story is accurate (and I have no reason to doubt that it is), then folks who haven't traditionally been prospects for HSA-type plans will suddenly become the only ones who actually qualify for them. But the very characteristics which made them less than ideal prospects (eg "what's my co-pay?") haven't changed, and won't change in the "new" environment.

'Tis a shame, really.

Underwhelming

As Bob noted last month, that seems to be the response of carriers to the upcoming Exchanges. Recall, though, that these are for individual policies; employers interested in group plan rates and products will access the "wholesale" version, SHOP (Small Business Health Options Program).

And shouldn't that actually be SB-HOP?

And as in the case of the aforementioned Exchanges, the reception by carriers has been - at best - lukewarm.

Case in point: Washington (the state, not Capital City).

"The board of the Washington Health Benefit Exchange is thinking about pushing the start date for the state's Small Business Health Options Program (SHOP) exchange to Oct. 1, 2014."

But, aren't those supposed to be online much sooner? As in, October of 2013?

Maybe, but you can't sell what you don't have, and thus far, a rousing one (1) carrier has expressed interest in participating. And that carrier, Kaiser Permanente, offers plans in only a limited area, not statewide.

There's a word for this....

Oh, yeah.

Thursday, May 16, 2013

I think I'm going to be sick

"The Internal Revenue Service official in charge of the tax-exempt organizations at the time when the unit targeted tea party groups now runs the IRS office responsible for the [ObamaTax]."

Words. Fail.

Chickens. Home. Roost.

From the "I told you so" files:

Back in January, we observed that, even though the ObamaTax had heavy union backing, there was some concern that these efforts might backfire:

"Union leaders say many of the law's requirements will drive up the costs for their health-care plans and make unionized workers less competitive"

Fast forward to April, and we see the wall start to crumble:

"A labor union representing roofers is reversing course and calling for repeal of the [ObamaTax], citing concerns the law will raise its cost for insuring members."

And now to complete the trifecta:

"Deep in the list of taxes that the [ObamaTax] will hit Americans with is a 40 percent excise tax on health plans typical union members have ... This tax will most directly affect union families and early retirees"

Schadenfreude - it's what's for dinner.

What could *possibly* go wrong - Part XXVII

A perfectly pleasant day, ruined:

"The [IRS] has requested funding for 1,954 full-time equivalent employees for its Affordable Care Act office in 2014 ... these bureaucrats will write and enforce tax regulations for parts of the economy in which they have no core competence."

Well, how is that any different than the way things stand now?

Oh, right:

"To monitor compliance with [the ObamaTax], the IRS and HHS are now building the largest personal information database the government has ever attempted ... The data hub will be used as the verification system for ObamaCare's complex subsidy formula. All insurers, self-insured businesses and government health programs must submit reports to the IRS about the individuals they cover, which the IRS will cross-check against tax returns."

So one wonders:

Will tax cheats be denied health care?


What if you accidentally underpay?

Who, exactly, is building this database? Is it at least an American company?

Given previous security breaches, it's not entirely certain that your data won't be misused or disseminated (ask the recent victims of the IRS non-profit certification process). And given that the Feds' reliability in matters data are, at best, spotty, one is also not reassured.

Sleep tight.

Kentucky Progress: The Gov self-destructs

Several weeks ago, we introduced readers to the efforts of one Bluegrass State patriot, David Adams, fighting against Frankfort's seemingly illegal efforts to install an ObamaTax insurance Exchange.

Now David has video of Gov Beshear apparently admitting as much:


Bravo, David!

Buying and selling HIPAA

HIPAA privacy rules regarding PHI (Personal Health Information) are pretty stringent. As an agent, I have to be careful about disclosing PHI even to clients' own family members.

Pause.

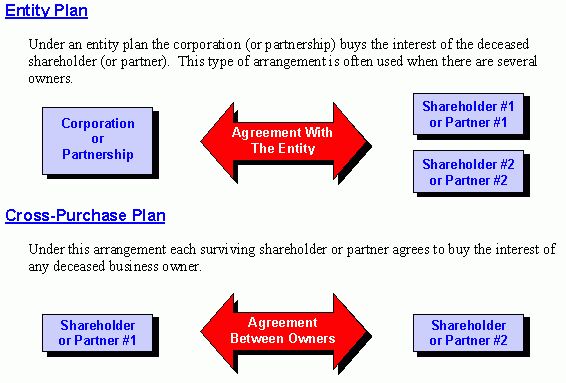
Buy-sell agreements (and other business uses of life insurance) are great risk management tools. If a partner or key employee dies, the business may suffer immediate financial losses which can be mitigated by the infusion of cash from a life insurance policy.

Pause.

Life insurance policies are contracts, and are required to adhere to certain standards and rules, one of which is that the application is part of the policy, and must be attached to (or enclosed within) it. The application forms the basis for the whole transaction, and includes not just name and date of birth, but pertinent health and financial information, as well.

Now, let's tie this all together:

Fred and Barney own Bedrock Widgets, and enter into a buy-sell agreement. They call me to purchase life insurance policies on each other to fund it. I take their applications and submit them to the Prehistoric Life Insurance Company, where they're underwritten and the policies issued. We meet, and I deliver the policies: Fred's to Barney, and Barney's to Fred.

See the problem?

Barney now has all of Fred's health info, and vice versa.

This could be....uncomfortable.

But is it against HIPAA regs?

Standard industry practice says no: the application is (by law) part of the application and by law a copy must be included in the policy. So carriers have - thus far - avoided having to address this seeming contradiction.

Thus far.

[Hat Tip: FoIB Brian D]

Wednesday, May 15, 2013

9 Terrifying Words

Who knew how prescient our 40th president would turn out to be?

The IRS - the folks tasked with enforcing the ObamaTax - are making the news (again) in a particularly disturbing way:

ObamaTax chow down

Whether it's movie theaters, theme parks or fast food joints, the ObamaTax is certainly taking a bite out of the employment market. As the Wall Street Journal notes:

"Some restaurant operators are scaling back expansion plans because of uncertainty about the expense of insuring employees under the [ObamaTax] ...  East Coast Wings & Grill, a 26-unit chain in North Carolina and Texas, in March imposed a three- to five-unit limit, for the time being, on the number of restaurants that franchisees can own, because of worries about health-care costs."

Ooopsies.

It's really a double-whammy: the costs themselves, plus the uncertainty of how they'll shake out. So businesses refrain from expanding, which in turn means fewer jobs are created, which in turn adds more drag to an already anemic economy.

And it's only going to get worse.

Over at Reason, there's a letter from an employer to his 23 employees laying out what they can expect in terms of changing health care policies and costs, and why. But here's the money quote:

"The higher cost for [the employer] would reduce our ability to hire, give raises, etc."

These are very real, very immediate concerns, but have been given short shrift in the legacy media. The letter is amazing for it's comprehensive but totally understandable explanation of where they've come, and where they're headed, by an employer who really "gets it." Read the whole thing.

See and Say and the ObamaTax

In addition to all the other wonderful ObamaTax news to which we've been treated lately, add this (Hat Tip: Assurant Employee Benefits):

Did you know that, come January, your ObamaTax-compliant "health" plan will also include "pediatric services including oral and vision care?"

Well, small group and individual plans will have to cover those, and you'll have the privilege of paying for those "benefits" (whether you want to or not).

These little "goodies" can have no annual or lifetime limits, must cover up to $700 per child (maximum of $1,400 per family - yay), and meet MLR requirements.

Click here to access the whole FAQ.

Cavalcade of Risk Number 183: Shaky Isles edition

Russell Hutchinson hosts this week's roundup of risk-related posts from New Zealand, and includes some interesting items from around the globe.

Do check it out.

Can you see it now, Kathleen?

"[H]enceforth insurers shall be forbidden by law to charge smokers higher rates than non-smokers. Smoking, as it turns out, “is a preexisting medical condition”

Tuesday, May 14, 2013

Kathleen, hear those locomotive whistles yet?

And now, from the Washington Post Wonkblog:
"Over the past three months, Sebelius has made multiple phone calls to health industry executives, community organizations and church groups and asked that they contribute whatever they can to nonprofit groups that are working to enroll uninsured Americans and increase awareness of the law"

Health news

■ First up, great news if you like Dom Perignon:

"[N]ew research  suggests three glasses of bubbly a week can improve your memory ... a regular tipple of champagne can help  prevent brain disorders such as dementia and Alzheimer’s disease."

Apparently, a compound found in certain grapes used in producing champagne - phenolic acid - can act as a memory aid.

Cheers!

■ In somewhat of a medical miracle, an Aussie who had been declared clinically dead for over half an hour was "brought back to life by a brand new resuscitation technique ... testing a mechanical CPR machine, which performs constant chest compressions, and a portable heart-lung machine -- normally used in theatre -- to keep oxygen and blood flowing to the patient's brain and vital organs."

And he wasn't the only one - there've been half a dozen others, as well.

■ Several months ago, Bob blogged on the intersection of ObamaCare and groceries. Fast forward a bit, and:

"Another group is objecting to another part of [the ObamaTax]: Grocers ... a U.S. health law provision that mandates the companies display the calorie content of all their foods."

The problem is that this adds huge costs to food production and distribution, threatening "a logistical nightmare."

Yeah, well, welcome to the club, laddies.

■ FoIB Holly R tips us to this story about cutting edge tech and a little girl:

"[D]octors at Children’s National Medical Center are making hearts. Not actual hearts, but three-dimensional synthetic models churned out by what looks like an ordinary printer."

While 3D guns are currently sucking up the media oxygen, these little wonders could save lives. Each organ is individually designed based on a patient's "particular intricacies and deformities" and then printed out and "installed."

Brave new world, indeed.

■ And finally, the story of Angelina Jolie's recent surgery is making the news, and it reminds me of a post we did at the beginning of the year:

"The 24-year-old Miss DC plans to undergo a double mastectomy ... removing both breasts as a preventative measure to reduce her chances of developing the disease that killed her mother, grandmother and great aunt."

Ms Jolie apparently shares some of the same concerns:

"[S]she underwent a preventive double mastectomy earlier this year after learning she carries a gene that increases her risk of developing breast cancer and ovarian cancer."

One presumes that, at some point, she'll deal with the potential of ovarian cancer in a similar way. I'm still somewhat conflicted about this kind of pre-emptive surgery, but have to admire the bravery of the women who face the decision, and for speaking out about it.

Monday, May 13, 2013

If you like your agent...

Remember back in the day, when we were promised "if you like your current plan, you can keep your current plan?" And remember how well that turned out?

Yeah.

Well, turns out that if you like your current agent, you may be able to keep him (or, of course, her). But probably not. From Anthem email:

"As part of our on-going support and commitment to you and your retention efforts, you will remain the Agent of Record for your clients when we transition them to an ACA-compliant off exchange* plan"

How nice.

Notice that little asterisk?

We'll get to that in a moment.

First, though, let's clarify what that term "transition" means. As we explained last month, existing plans will be going away shortly (what, you thought they meant it when they said you could keep your plan?), and currently insured folks will be "mapped" or changed over to comparable ObamaTax-compliant ones (and by "comparable" we mean "nothing at all like"). Don't like that idea? Please let Mr Baucus know.

Once you've been "mapped" to your new plan, you may have some questions about it, so you'll likely want to discuss those with your agent.

And now for that pesky little asterisk:

"You may be required to become Exchange Certified if your client enrolls via the Exchange"

And if your agent (rationally) take a pass on that attractive offer? Well, then, time to pick a new one. Of course, that likely means someone whom you don't know, have never known, and have no relationship with. Not to mention, someone who may, in fact, be completely uninterested in helping you.

Feel better?

What could possibly go wrong?

So Ms Kathleen, under fire for her clumsy, expensive implementation of the ObamaTax, has decided to strong-arm encourage the folks on whom she's counting to provide the actual products for the Exchanges:

"Health and Human Services Secretary Kathleen Sebelius is asking companies for financial donations to help implement President Barack Obama's healthcare overhaul"

While this is every bit as sad, pitiable and contemptible as it appears, I have another question:

How legal would such a donation be?

After all, there's that little box on our tax forms for donations to the presidential campaigns, and of course individual citizens are allowed to pay more in taxes than they actually owe.

But how, exactly, can corporations do this? When individuals "contribute" by electing to pay more, they can't specify that these extra dollars go to specific agencies.
One supposes that corporations can also choose to pay more, but again, that's going to a general fund, not a specific agency or effort.

So how does XYZ Mutual actually do this (if they're so inclined)?

And speaking of tax forms, yours just got more complicated:

"When Obamacare’s individual mandate takes effect in 2014, all Americans who file income tax returns must complete an additional IRS tax form ... will require disclosure of a taxpayer’s personal identifying health information in order to determine compliance with the [ObamaTax[ mandate."

So not only will these wunderkinds have access to your personal financial data, but now your health data, as well.

Warm fuzzies, anyone?

Pharma whines their bills won't be paid in full

Now that excessive hospital billings are getting some press maybe Journolist, or those masquerading as them, can stop writing articles about the high out of pocket cost of Rx and start asking why the Rx are so expensive to start with:

"Cancer patients could face high costs for medications under President Barack Obama's health care law, industry analysts and advocates warn."

Some exchange plans might require members pay 30% of drugs that cost $10K per month and this concerns the pharmaceutical companies. All of us should be concerned about the other $7K we are paying.  The expanded marketing of Enbrel which can cost a couple thousand a month should also be of concern to all of us.

Enroll America will not be Enrolling


A recent post in Health Affairs written by Enroll America's top officials discusses the role they will play in educating and enrolling consumers into insurance exchanges. Interestingly, their post made no mention of Navigators. So I decided to reach out to the authors in the comment section. Here is what I asked:
I’m curious if Enroll America has filed with HHS to serve as Navigators? Could one of the authors please respond? Thank you!
Finally I received a response. This wasn't posted in the article but came direct to my email from Ron Pollack of Families USA who is also the Founding Board Chairman of Enroll America.
Enroll America  has not filed to serve as navigators and has no intention of doing so.
So there you have it. The group that is supposed to be leading the charge to serve those who need it most won't be serving them much at all.

Friday, May 10, 2013

Friday Afternoon LinkFest

■ First the bad news. From the Annals of the Much Vaunted National Health System© comes this alarming development:

"Almost half of Britons say they or their families have experienced poor care and neglect at the hands of the [MVNHS©] ... Despite tens of billions of pounds being invested in the NHS, 46 per cent of respondents said they thought standards of care had declined over the past ten years"

Welcome to the future of American health care.


■ On the other hand, scientists at the Boston Children's Hospital have developed a "micro-particle that can be injected into your bloodstream to oxygenate your blood – without any help being required from your lungs."

This could be quite useful during certain surgical procedures, among other uses.


■ And, finally, something of a mix of good and bad news. A 14 year old student's science fair project found that the magnets in iPad2 units can "interfere with life-saving heart devices ... The research offers a valuable warning for people with implanted defibrillators."

Good job, Gianna!

Oh, the kicker? She didn't even take first place in the fair.

So Kathleen, how's it going? [UPDATED]

Colorado has spent $61 million to set up its ObamaCare Exchanges. Colorado is now asking you for $125 million more.

And California law does not even require full disclosure of how much it is spending.

The Two Locomotives Greet One Another

UPDATE [HGS]: To go along with the Centennial State's Exchange woes, and the Golden State's lax "enforcement" rules, we have this from Ms Kathleen's little fiefdom:

"States have until [today] to decide whether they want to keep their state-run Pre-existing Condition Insurance Plan (PCIP) programs running or kill the programs and put the enrollees in the hands of the federal PCIP system."

Here's the thing: we reported a while back that the PCIP program had already wound down, so how is it that it's still thrashing about?

Stranger Danger Part 2

Who would have seen this "train wreck" coming? While there have been many PPACA related alerts already issued this one comes from the Buckeye State.

Consumer Alert! Ohio Department of Insurance Director Mary Taylor issued a consumer alert yesterday. Scammers are reaching out to consumers telling them they are part of the new health insurance exchanges.

The scam involves people acting as government representatives (think Navigators) and telling potential consumers that they are "authorized to help people navigate the health insurance exchange created under the ACA and say they need to verify the person’s name, address and Social Security number."

ODI says to avoid becoming a victim people need to protect their personal information AND that government program representatives do not make house calls or solicit by telephone.
 
So how exactly will Navigators be able to reach out to potential consumers if they can't solicit by phone or go door to door?

Cavalcade of Risk #183: Call for submissions

Russell Hutchinson hosts next week's Cav. Entries are due by Monday (the 13th).

To submit your risk-related post, just click here to email it.

You'll need to provide:

■ Your post's url and title
■ Your blog's url and name
■ Your name and email
■ A (brief) summary of the post

PLEASE remember: ONLY posts that relate to risk (not personal finance tips and the like). And please only submit if you are willing to link back to the carnival if your submission is accepted.

Thursday, May 09, 2013

$Chump $Change?

So here's a question that's been nagging at me for a while:

If the ObamaTax is such a great deal, such an outstanding idea, then why, almost 4 years after it was passed, does it need high-pressure sales tactics to enforce encourage participation?

First, Matlock weighed in with a folksy enticement that misrepresented how the ObamaTax would work. At over $3 million for his efforts, one might have thought that he could afford a new suit.

Now, HHS Secretary Shecantbeserious is spending 50 times that in a new "outreach" effort:

"[Ms Shecantbeseerious] announced Thursday a plan to help uninsured Americans find coverage under the new health care law by offering $150 million to community health centers ... part of a broad push to promote [the train-wreck], as calendar pages fall away toward key dates to implement the law."

The esteemed Ms Kathy opined that it "won’t be easy" (surely an early contender for understatement of the year), but that it "has huge benefits for the American people."

Again, if that's true, why the $150,000,000 snow job?

Really, David?

A while back, we took my good (blog-)friend David Williams to task for his characterization of the role of agents in the field of health insurance. Recently, David forayed once more into the general area, writing about the ObamaTax MLR (Medical Loss Ratio) rules:

"I’d like to see us learn from implementation of the law and make improvements along the way. Unfortunately many opponents take the opposite view –and would still rather repeal the whole law or resist implementation ... In the spirit of improving the law, I’d like to see a modification to the minimum medical loss ratio rules for health plans ... After all, if medical costs are contained “too much” then the plan has to pay a rebate."

He then offers this suggestion:

"[L]et plans with a strong track record of cost containment escape the MLR, at least partially."

I'm very fortunate to have access to some of the best brains in the blogosphere [ed: can't you just call them co-bloggers?]. While I do have my own take on David's post, I turned to them for in-depth analysis.

I was not disappointed:

Patrick noticed that David is using the same talking points we heard in 2010 by the WH and Congressional D’s such as “negotiating hard with providers, introducing better network designs, and improving payment methodologies.” All of these things are being done and none of it has to do with MLR. So I’m really not sure why he thinks that lowering something he already hates will help keep rates in check.

In fact, Patrick writes, one of David's old blog posts from early in 2012 was titled “I don’t really want my $127 medical loss ratio rebate” His argument then was that MLR creates a perverse incentive for insurers to hit the required levels by not doing what they are paid to do. He states that this would be done by eliminating cost containment measures.

Um no, cost containment measures create competition. Lowering the 80% MLR and increasing the 20% for administration would potentially drive costs down. Last time I took an economics course I was taught that lowering the 80% would be more valuable than lowering the 20%. Especially when the largest variable is the 80%.

Patrick was also unimpressed with David's example of undercutting the market by either raising premiums by less than the market rate or CPI:

The average profit margin in the health insurance industry is around 4%. If MLR requires a company to spend 80% on claims and 20% on everything else then the 4% is already budgeted into the 100%. So next year the “average market rate increase” is 5%. Insurance Company A’s loss ratio was on target at 80% and  made their margin of 4%. This year some unknown government entity says that because Insurance Company A undercut the market and offered at 3% increase they have the ability to reduce their MLR requirement by an extra 5%.

Here are the best case and worst case scenarios:

Best case: The loss ratio is 70%. Insurance Company A must rebate 5% to consumers and makes a profit of 9%. Rates for next year go up by the “average market increase”. Why? Because the company under this design is able to keep a higher profit and still must rebate consumers. Net result = price of insurance to the consumer still goes up.

Worst case: The loss ratio comes in at 85%. They lose 1% (which is what they would have lost under the original deal of 80%). End result here is that Insurance Company A will receive reinsurance pool funds to offset their losses and will still increase their rates to the consumers.

Win-win Not the outcome David's expecting.

Wednesday, May 08, 2013

Kentucky Progress: A Study in Persistence

A while back, I became acquainted with David Adams' work in fighting Bluegrass State "city hall" politics, specifically Kentucky's governor Beshear's efforts to install a state-run Exchange.

The issue is that, according to David's take on Kentucky state law, the Gov had no legal right to do so.

So David sued him.

Now, one might be tempted to think of windmills and Don Quixote here, but David is serious, committed and resourceful. I've been looking for a way to introduce him and his project to IB readers, and he's thoughtfully provided a summary post ("the plot so far" ) to give a basic background of the issues and his strategy.

Here's a taste, but read the whole thing:
"Kentucky Governor Steve Beshear wants to win his fight for assuming the ObamaCare unfunded mandate without addressing funding or mandates ... The Kentucky Health Benefit Exchange will be funded "from revenues generated by the Exchange" according to Beshear's executive order ... By itself, this action violates the rights of taxpayers to not have their pockets picked without legislation first being properly enacted."
This is important, grass-roots stuff. Click on over for the whole story.

Penn Treaty Update

It's been about almost exactly a year since we last checked in on the troubled Long Term Care insurance carrier. At the time, the Keystone State's Commonwealth Court had barred regulators from liquidating the company, insisting that it be "rehabilitated."

Fast forward twelve months, and it looks like there's finally a plan in place to do just that:

"The Pennsylvania insurance commissioner is seeking court permission to rehabilitate Penn Treaty ... in ways that could lead to big cuts in benefits, or big increases in premium rates, for the company's long-term care insurance (LTCI) policyholders."

Benefits cuts or rate hikes?

Count on both.

The carrier seems to be about $2 billion in the hole, and "has less than $1 in assets for every $3 that it should hold as reserves." Oopsies. And it's estimated that they'd have to jack up premiums by 300% to make up the shortfalls. Ouchies.

Some of the alternatives include increasing elimination periods to at least 90 days (which is pretty much industry-standard for new plans now), capping benefit periods and dialing down inflation protection increases.

Thing is, policyholders who've hung on this long probably don't have a lot of choices: those that could bailed early, those still on are probably stuck.

Doesn't seem like this will end well.

Tuesday, May 07, 2013

Crystal Ball vs ObamaTax

Here's the thing: the ObamaTax doesn't "bend the cost curve" so much as it distorts the health care delivery and financing market. Case in point:
"[T]he hospital where I was born, in a small coal-mining and smelting factory town outside of Pittsburgh ... relies heavily on Medicare and Medicaid payments, and it’s going bankrupt.

[A]s of April 30, Blue Cross in western Pennsylvania will be transforming itself from being an insurer to actually owning and running hospitals and labs -- and having medical staff on the payroll."
We used to call this a staff model HMO (Thanks, Ted!) and quite a few or them popped up in the 80's. Now we've apparently come full circle. I don't think there's anything intrinsically evil about these arrangements, but they do call into question the role of "choice." That is, if the insurer is also the provider, there's a strong incentive (and concomitant ability) to keep things under tight control.

And, of course, there's the little matter of cash:

"One of the first changes the new management has requested is a 30 percent increase in reimbursement rates for this year, with 10 percent annual escalators to follow."

Since we already know that health care costs drive health insurance costs, this will mean significant premium increases for those who actually pay for private insurance. This is nothing new, really: as the article notes, those of us with insurance have always subsidized those on public plans. The problem now becomes how that's going to play out under the ObamaTax, with its tens of millions of new Medicaid participants. Think of it as squeezing a balloon:

The air (money) has to go somewhere, else it will pop.

Hmmm.

The President and The ObamaTax: Cluelessness abounds

Recently, the President had this to say about his signature legislation:

"A huge chunk of [the ObamaTax has] already been implemented."

Really?

Let's go to the videotape [ed: metaphorically, of course]:

■ Child-only insurance policies gone? Check.


■ PCIP crashed and burned? Check.

■ Birth control Convenience items mandated, adding to costs and infringing citizens' 1st Amendment rights? Check.

■ ObamaWaivers for unions, which are now bailing on the train wreck? Check. 

■ 3000% rate decreases (not)? Check.

■ Medical device tax bankrupting companies and inhibiting breakthroughs? Check. 

■ Class act abandoned as unworkable and unsustainable? Check.

Awesome roll-out, dude.

Monday, May 06, 2013

More circular reasoning spinning around the ObamaTax

A few weeks ago, we highlighted the, um, interesting logic employed by soon-to-be-former Senator Max Baucus on why he now views the ObamaTax as a "train wreck."

Today's example comes to us via FoIB Holly R, who sent us a link purportedly explaining why Golden State politicos are pushing back against smoker surcharges in their Exchange-based ObamaPlans.

No, that's not a typo: these rocket surgeons want to prohibit carriers from charging smokers more because, well, in their own words:

"[A] surcharge for smokers would mean they wouldn't get the benefit of the subsidy that's supposed to make buying insurance through the marketplaces in 2014 more affordable ... If the state opted for the maximum surcharge, health insurance would become unaffordable for those with the lowest incomes ... it's that group that's most likely to smoke."

You cannot make this stuff up.

Boston and One Agent's Experience

Read the whole thing.

Here's a taste:
"For Jeff Breese, a Chartered Retirement Planning Counselor at Flores Wealth Management and Raymond James in Chandler, Ariz., this year’s marathon was a culmination of many things and a homecoming of sorts ...

Breese is in the business of helping people prepare for the unexpected ...

Breese will go back to work with an acute awareness of the importance of what he does for a living, and with a medal for finishing the marathon."

ObamaTax Jailbait

So it turns out that there's (at least) one bunch of folks who will benefit mightily from the new "healthcare" law:

"Starting in January, many of the 650,000 inmates released from prison each year will be eligible for something else: health care by way of Medicaid, thanks to the [ObamaTax]."

Not to worry, though, that's a fairly small number of miscreants who'll have access to healthcare on your dime.

Wait, what?

"A sizable portion of the nearly 5 million ex-offenders who are on parole or probation at any given time will also be covered."

Luckliy, there's a silver lining for those of us who manage to stay on the right side of the law:

"It potentially revolutionizes the criminal justice system and health system"

Oh, goody.

Friday, May 03, 2013

Talk about bold, fresh ideas . . .


I have just read this remarkable commentary on Medicaid from Avik Roy at Forbes. 

Mr. Roy discusses the most recent results of an ongoing analysis of Medicaid costs in the State of Oregon.  This is important for many reasons, not least being the fact that ObamaCare hopes to reduce the number of uninsured by extending Medicaid coverage.  I think Obamacare chose this strategy because, overwhelmingly, the lack of medical insurance is a creature of poverty – and Medicaid is the government medical insurance program for the poor. 

I urge you to read Mr. Roy’s entire comment.  This passage near the end strikes me as an especially bold and fresh breath of air:

“Let’s build a new health program for low-income Americans, one that pays primary care physicians $150 a month to see each patient, whether they are healthy or sick . . . Hell, put the entire country on that kind of plan, along with giving people the opportunity to use health savings accounts to cover the rest.”

I think this is a great idea especially the idea to put the entire country on a uniform primary care plan.

The taxpayers would share the cost of every citizen’s primary care up to an annual amount - $1,800 in this example.  That number could be adjusted in the future as necessary to keep up with reasonable increases in the cost of delivering such care. 

This plan would establish a basic level of primary medical care guaranteed to every citizen.  Individuals and families could then purchase insurance for catastrophic medical events on top of that, at their own expense.  I think it would be necessary for the taxpayers also to subsidize the catastrophic insurance subject to a sliding income scale.  People who can afford full or “comprehensive” coverage beyond that may simply go ahead and buy it – at their own expense. 

Paying PCP’s $150 a month for every American patient they see would cost about $567 billion per year.  Isn’t that about half the annual cost of Obamacare?  Of course that cost would rise as population rises and as medical costs rise.  But, still . . . Obamacare’s cost will rise too.  So isn't this a more effective and less costly approach?

btw, I think a $2,000 per person calendar year deductible is a little light – I’d suggest $3,000 accompanied by an HSA.  But now we’re just quibbling about how exactly we will drain the swamp.

Thursday, May 02, 2013

An Open Letter to Max and Tom

Dear Senator Harkin and Senator Baucus:

Recently you both have made comments with unfavorable views on how dollars from PPACA are being spent. Senator Baucus, you have characterized the law as a "train wreck" and put outreach and education as your top reason why people aren't engaged. Senator Harkin, you have chastised the White House and HHS for continuing to take money from the Prevention Fund and using it for implementation of the law. Both of these concerns are legitimate.

As a professional health insurance advisor I help design benefit plans, resolve claims disputes, conduct educational meetings, facilitate enrollments/terminations, solve billing issues, and help clients comply with complex state and federal laws like HIPAA, ERISA, and of course, PPACA.

Being a member of this profession requires proper licensing and a stringent continuing education program including course work and testing. We have ethical and moral obligations to our clients to always serve in their best interest and we also must carry professional liability insurance as a protection to the consumers we advise.

Here is a solution that solves your concerns and won't cost the federal government a single dime. Not only that, but it will provide job security to hundreds of thousands of people. The solution is simple. First, engage health insurance professionals to aid in the outreach, education, and enrollment. Second, eliminate the role of Navigators.

Health insurance professionals are always looking for new clients. We already have the business model built. Use our marketing and education tools to generate interest in purchasing health insurance. We compete to earn the business of those we educate on the options they have available. Instead of adding another layer of bureacracy and cost into this "train wreck" (your words not mine Senator) why not strengthen a profession of private sector business people? It makes way too much sense not to.

Health Care Lottery

I thought this looked familiar:

"In 2008, Oregon expanded its Medicaid program, but because the state could not cover everybody, lawmakers opened up a lottery that randomly drew 30,000 names from a waiting list of almost 90,000 and allowed them to apply for the program. This created a unique opportunity for health researchers, ultimately allowing them to compare the health outcomes of 6,387 low-income adults who were able to enroll in the program with 5,842 who were not selected."

We actually covered this at the time:

"Oregon decided to enroll an additional 10,000 people in its Medicaid program via lottery ... Granted, one year is hardly long-term, but shouldn't there have been some indication of improved morbidity (if not mortality) even in the short-run?"

As it turns out, both Michael and we were correct:

"[R]esearchers found that those who enrolled in Medicaid spent a lot more on medical care than those who weren’t able to enroll, but didn’t significantly improve their health outcomes."

Ooops.

The problem, of course, is that taxpayers spent all this money and there's very little to show for it.

La plus ca change...

Oh - and lest we forget, Barbara Wagner is still unavailable for comment.

Fox Butterfield on the ObamaTax

The Wall Street Journal's James Taranto has a regular feature wherein he uses the "Fox Butterfield Effect" to demonstrate the mind-boggling density of folks who consistently confuse cause with effect ("the prisons are full, despite a decreasing crime rate").

Here's a mild example directly related to the train-wreck:

"Employer spending on benefits rose at the slowest pace on record in the first quarter, as companies began bracing for higher health costs with next year's launch of [the ObamaTax]."

The folks at IBD do get it right when they note that many "modest-wage" employers will be among the hardest hit. Of course, it's their employees who will be the worse for wear, since they'll be forced to buy insurance (often unsubsidized) at rates that are far higher than even today.

And it's getting worse:

"Total benefits in service occupations shrank 0.3% in Q1, the first decline in data going back to 2002."

Ooops.