Friday, November 16, 2012

Oklahoma, Okay?

A month ago, Bob posted on a "unique practice at the Surgery Center of Oklahoma" which accepts only cold, hard cash on the barrel head.

No insurance, no Medicare or Medicaid, no third party payors of any kind.

So, how's that working out for the folks who run the joint?

From the horse's mouth:


[Hat Tip: Hot Air]

Thursday, November 15, 2012

Consequences and Eddies

The fallout from the recently affirmed Not So Vaunted Health System© continues to build. And it's not just pizza, but a host of seemingly unrelated institutions.

FoIB Jeff M tips us to the recent announcement by Wake Forest Baptist Medical Center, which has recently axed almost 1,000 employees as a result of "the challenges of health-care reform, federal budget deficits and a decline in research funding from The National Institutes of Health and private industry.”

But it's not just the Baptists. At the other end of the spectrum, "the Roman Catholic church will not comply with the Obama administration requirement that most employers provide health insurance covering birth control." This is in response to the convenience items birth control mandate handed down by HHS Secretary Shecantbeserious.

And the hits just keep on comin': Palm Beach, Florida restaurateur John Metz has come up with a novel way to unbundle the extra costs of the NSVHS©. He's planning to "charge his customers a five-percent surcharge and decrease his employees’ hours to offset the costs of Obamacare on his businesses."

That's really a two-fer: by specifically noting the extra charge, customers get a real-world intro to the extra costs the train-wreck imposes on business. And servers get to see the effects of these costs on their own lives, both in terms of fewer hours (and lower net pay) and, presumably, lower tips (and thus lower net pay) as customers decide how much that service is worth versus the surcharge.

Talk about a Grand Slam.

Merp, Merp!

Hard to believe, but we really haven't covered Medical Expense Reimbursement Plans (MERPs) much here at IB. Back in August, Nate alluded to them when discussing small group plans and Health Reimbursement Arrangements (HRAs). MERPs allow an employer to help employees pay their health insurance premiums (among other things). Hamilton County (OH) is trying one out in an effort to manage its out-of-control health insurance costs by encouraging its employees to bail on the County plan in favor of a spouse's (or another job's).

It's kind of a neat deal, actually:

"Hamilton County, which employs about 4,000, is doing everything it can to prevent layoffs ... The MERP Hamilton County is implementing is a bit different from a traditional MERP ... The plan reimburses medical expenses incurred under “alternate coverage”

To get the full benefit of the plan, an employee has to waive off the County insurance plan in favor of the aforementioned spouse's or other employer-based health insurance plan. Interestingly, that plan cannot be a Health Savings Account. No can do? Fine, then stay on the County plan, but count on getting dinged more on your premiums.

And there's this: in addition to reimbursing an alternate plan's premiums, the new MERP will also help towards that plan's out of pocket expenses (deductibles, co-pays and the like). Even with all that, the county is looking to save upwards of $3 million next year.

Getting folks off group plans isn't new - we've seen this trend for a while. But it's generally been a "if you can go on your spouse's plan, you must go on it" type of deal. This "carrot" instead of "stick" approach may be the next big thing.

Thanks, Bob, for the tip!

Wednesday, November 14, 2012

Um, D'unh?!

I don't get why this would be "news:"

"Obamacare to Jack Up Insurance Premiums ... According to a survey from the National Business Group on Health, employers  expect their health insurance costs to increase 7%."

Hey fellas? Stop inhaling: only 7%? You wish.

And this:

"60% of those employers plan to ask workers to pay higher monthly premiums."

Also ignores reality. As we pointed out many years ago:

"Companies do not pay taxes, and they do not pay for health insurance.

In case you missed that, let me repeat: Companies – businesses – pay neither taxes nor insurance premiums.

Companies do collect (sales) taxes, and pass them on to the states in which they do business. They also include any business taxes due in the price of the product or service. They pay employees a portion of their salary, and forward the balance to the insurance carrier (and/or state government).

They do not actually pay the taxes, nor the insurance premiums
."

So this whole notion that employers are going to be asking what employees they have left to "contribute" more towards their premium is silly. And it ignores the fact that a lot of employers will be dumping either full-time employees or their group health insurance plans. Or both.

Of course, we'll continue to hear about how it's all the fault of business, but the reality is that businesses exist to make money, not to pay increasignly high labor costs (such as health insurance premiums). And now that our own Not So Vaunted Health System© (nee: ObamaCare) has been affirmed, this is just the beginning.

Kinda wish we'd read it before they passed it, no?

Can you hear me now?

The Brits' Much Vaunted National Health System© (MVNHS©) has long been a passion of ours, for (mostly) obvious reasons. The latest installment in the long-running joke that is the MVNHS© demonstrates what happens when physicians answer to bureaucrats:

"Doctors are failing to really listen to patients' views on how they want to be treated ... Involving patients in discussions about treatment could cut the cost of healthcare around the world"

Now, I'd take issue with that last - after all, "the world" is a pretty big place, and that which works in one country or culture might not translate so well to another - but the greater point is that docs in government-run health care schemes are accountable to the government, not their "patients." Indeed, since the government pays the bills, the patient really has little (if any) say.

The problem is that the payer (government) isn't the patient, who may well know best what it is that needs to be done:

"[P]reference misdiagnosis" - misinterpreting or ignoring the patient's wishes - is a significant problem which is damaging to both doctors and patients ... it can lead to, what they call, "silent" misdiagnoses - when doctors choose the wrong treatments because they fail to assess their patients' preferences correctly."

This was one of the most important aspects of consumer-driven health care (now outlawed under our own Not So Vaunted Health System©): transparency and financial empowerment (the premise and promise of Health Savings Accounts) did, in fact, rely to at least some extent on the patient's engagement with their provider.

As under the British system, the absence of this interaction can lead to devastating consequences:

"In one study they looked at, doctors believed that 71% of patients with breast cancer rate keeping their breast as a top priority, but the figure reported by patients was just 7%."

Of course there are trade-offs (life is, after all, a series of them), but divorcing the patient from his or her own care decisions seems a pretty drastic one. Of course, the person (or institution) with the gold makes the rules (cf: IPAB Death Panels).

[Hat Tip:Dr Dino Ramzi]

Cavalcade of Risk #170: Risky Business

Louise Norris at Colorado Health Insurance Insider presents an outstanding Cavalcade this week. Interspersed with risky quotes and photos, it's obvious that she's read all the entries, and provides helpful context for each one.

Do check it out!

Tuesday, November 13, 2012

Yet another example to why we should end entitlements as we know them...

From CNBC:

"Harris, a 22-year-old smoker, was set to see his cost per paycheck rise to $29.60 from $25.40. He says he has decided not to sign up for coverage. Given his low income, as Harris foregoes coverage any major medical bills could potentially fall to taxpayers through the government's Medicaid program."

$4.20, a pack a week? Maybe three packs a month and he drops insurance. Because he is busy engaging in activity that makes him more expensive to insure he can't afford insurance so the rest of us that are working get to pick up the tab.

Welcome to the Welfare State, get comfortable.

Vikings and The NSVHS©

Back in the day, Norway was known for Edvard Munch, Sonja Henie and Leif Ericson. But even the reviled Vidkun Quisling is most likely whirling in his grave over the current state of Norway's "health care" system:

"A man – let’s call him Joseph K. – is slicing up a cucumber when he suddenly cuts off the tip of his thumb. He hastens to the E.R., where a doctor clips off the finger of a plastic glove, pours antibiotic into it, slips it over the thumb, then wraps a bandage around the entire finger."

Ouch, but it gets worse. Fast forward a couple days:
"...the E.R. is simply not open at this hour. Until 3:30 P.M., the E.R. operates out of another location in the small, relatively remote town ... make an appointment if you insist, but you should know – there’s not always a doctor here!”

“What? There’s not always a doctor at the E.R.?”

“Yes, there’s not always a doctor here!”
Such is care under the Norwegian government-run health care system. Regular IB readers won't be surprised to read this, but it's what we have to look forward to under the recently affirmed NSVHS© (Not So Vaunted Health System©), formerly known as ObamaCare. When the government runs things, there are always shortages - of doctors, medicines, hospital beds, you name it.

Well, to be fair, not everything is in short supply: nameless, faceless, unaccountable bureaucrats are rife (if not readily accessible). As Bob's noted on many occasions, this kind of system is a real bargain - until you need it.

[Hat Tip: Joe B]

Monday, November 12, 2012

Shecantbeserious backpedals

Hurry up and wait:

"Health and Human Services Secretary [Shecantbeserious] said in a letter to governors Friday that she still wants to hear by the end of next week if states will be setting up new health insurance markets under the law ... states can now take another month, until mid-December, to submit detailed blueprints."

Those of the 58 states that are looking to partner up with DC for their Exchanges have until next February. Or later, one supposes, since there's really very little Mme Secretary can do to make them fall in line.

Which is perhaps a good thing, since at least one state (and likely several others) are going to find it, um, challenging to comply.

How's that, Henry?

Well, as Cato's Michael Cannon reports, "operating an ObamaCare exchange would violate [Ohio's] constitution."

This would seem an insurmountable problem, but there may be more to it. As it's Veteran's Day, I've had to put off until tomorrow my call to the Ohio Insurance commish asking about how this might play out. Looking forward to posting any results forthwith.

Medicaid solution for State Finances

As I am stuck doing all too often these days, I was reviewing some segments of PPACA for clients. An idea struck me on how to solve State spending and budget issues. Now that 1 in 5 people are covered by Medicaid, States are going to be forced to spend more of their limited finances on this healthcare plan.

According to Kaiser State Health Facts Ohio spent around $6,116 per Medicaid Enrollee in 2009. 

http://www.statehealthfacts.org/profileind.jsp?sub=47&rgn=37&cat=4

Drop Medicaid. Before anyone screams how unfair and cruel that is I'm not saying leave them without coverage, Obama said PPACA will make HealthCare affordable, so take him up on it.

"The Premium Credit" is available to people with incomes up to 400% of the Federal Poverty Level (FPL). For 1, 2, or 3 person households that is $44,680, $60,520, and $76,360 respectively. They would be required to pay between 2% and 9.5% of their income. Using 400% FPL and 9.5% maximum sharing cost the individuals would be responsible for;

#     Max Cost      Current OH Cost          Savings to the State
1 = $4,244.60      $6,116.00                            $1,871.40
2 = $5,749.40      $12,232.00                          $6,482.60
3 = $7,254.20      $18,348.00                          $11,093.80

The State could turn around and give vouchers to the residents to cover their liability under the exchange. It would cost the resident nothing. The resident would have considerably better coverage than Medicaid. The State would save billions. Doctors and Hospitals would be reimbursed at Private Insurance rates instead of Medicaid rates. There is enough savings left over they could even give employers $2,000 tax credits to offset their penalties, assuming anyone even employs more then 50 people come 1/1/2014.

Everyone is a winner...well except the Federal Government, but they'll just print more money anyways so it doesn't really even affect them.

Sunday, November 11, 2012

Debate on Gov role in Healthcare already gone?

Many people disagree with the current and further intrusion into our healthcare by Government. They say government is taking too active of a role in what should be a personal matter. On my way to the office this morning I had the realization this argument might already be long gone.

For a brief moment driving to the office I was stuck behind the town leaf vacuum. For those not living in parts of the country with lots of trees, there is a city truck that drives around vacuuming leaves from people's yards. If we have outsourced such trivial matters as raking leaves to the government, managing our own health must no longer be possible.

In an ironic twist healthplans now pay us to exercise, i.e. to do something like raking the leaves. I think it is a short matter of time until we have cap and trade for calories. Don't worry I'm sure for a small fee we will be able to buy burned calorie credits from someone more willing to rake the leaves.

Friday, November 09, 2012

Fraudulent Agent Tricks

While most insurance professionals are just that, it's not always the case. As we saw not long ago, there are unethical agents out there, and sometimes they make the news.

Of course, it takes a special kind of stupid to defraud one of the best-known names in American culture, but that apparently didn't stop California insurance agent Jerry Goldman from trying:

"A Southern California insurance broker was arrested Wednesday on allegations he overcharged Tom Hanks, musician Andy Summers and others hundreds of thousands of dollars for insurance premiums."

Generally speaking, only the US Government is allowed to overcharge folks for insurance premiums.

According to the story at the link, this little game has been going on for over 13 years. It appears that he overcharged his clients, remitting the actual premium due to the carrier(s) while keeping the difference for himself.

One rarely (if ever) sees this on the life and health side, since the premiums for these types of plans are almost always submitted directly to the carrier, or at least with checks made payable to them. On the P&C side, though, this isn't always the case, which is why this kind of mischief can occur.

Credit where it's due, however: at least the agent submitted the proper premiums, so that the coverage was (presumably) in force had a claim occurred. The coverages ran the gamut from cars and property to worker's comp and fine art.

Health Wonk Review: Post-election edition

HWR co-founder (and all around good guy) Joe Paduda hosts this post-apocalyptic election round-up of posts from around the health wonkosphere. There's a lot of information, speculation, adulation and frustration, but well worth clicking through for an idea of what's in store health policy-wise.

Cavalcade of Risk #170: Call for submissions


Jay Norris next week's Cavalcade of Risk - Entries are due by Monday (the 12th).

To submit your risk-related post, just click here to email it.

You'll need to provide:

■ Your post's url and title
■ Your blog's url and name
■ Your name and email
■ A (brief) summary of the post

PLEASE remember: ONLY posts that relate to risk (not personal finance tips and the like). And please only submit if you are willing to link back to the carnival if your submission is accepted.

Thanks!

And that's that: Introducing....

According to erstwhile House Speaker John "Boom Boom" Boehner:

"It's pretty clear that the president was reelected, Obamacare is the law of the land."

Fine.

So begins a new chapter here at IB, as The ObamaTax becomes the Not So Vaunted Health System©. The NSVHS© is characterized by guaranteed issue insurance, which guarantees only that rational people will wait to buy their policy until they're in the ambulance. It means that rational people will look at the fine penalty tax of a few hundred or so dollars and deduce, quite rationally, that paying thousands of dollars for a policy when one is well makes no economic sense.

Rational people will understand, of course, that actual health care will, of necessity, become rationed as a direct consequence of other folks being subsidized to buy new policies, creating ever more increasing demand, even as provider reimbursements falter (a consequence of the $700+ billion Medicare cut).

Rational employers will understand that the $2000 per employee fine penalty tax is also a bargain compared to the tens of thousands of dollars group plans will now cost as a result of things like the "Mercedes" er, "Cadillac" tax and other such goodies.

It means that health care quality will decline, as will new medical tech. It means that seniors will have fewer choices, perhaps not even the choice of whether to live.

Over the next few weeks and months, Mme Secretary Shecantbeserious will begin to roll out all the new rules and regs that will dictate how the government will direct our your health care.

Not with a bang, but a whimper...

Wednesday, November 07, 2012

From the P&C files: BizInt coverage

Business Interruption coverage helps pay the bills when your store or plant are shut down because of some natural or other disaster. When we think about business insurance, we usually think about fire damage, or flooding, that kind of thing. And of course that's important. But what we may not think about is how the business itself can continue as a result of a catastrophe.

Hurricane Sandy provides an excellent object lesson in how this important coverage works. The folks at Allianz Global Corporate & Specialty has come out with a new study -  “Managing Disruptions” - that "explores how businesses and insurers are re-examining their exposures to business interruption and supply chain risk."

As a friend of mine is fond of saying, we are all connected. So it's not just about a given business, but its place in a supply chain and how that can disrupt other businesses up and down that chain.

It's an interesting subject, and a glimpse into an area of risk assessment and management that we don't often get.

[Hat Tip: Annika Schuenemann]

Medical Tourism and the ObamaTax

Now that the ObamaTax has been affirmed, it's time to look ahead. This means a shortage of providers and major increases in both premiums and health care costs. There's not much one can do about the increased premium side of the equation, but there are indeed ways to mitigate both the provider shortage and increased cost of care.

While medical tourism has been around a while (we first posted on the phenomenon over 6 years ago), it seems poised to really take flight under the ObamaTax regime:

"US patients obtain health care treatment in foreign countries well below US rates. Treatments include dental implants, hip and knee replacements or bariatric surgeries. Americans also go abroad for more complicated procedures such as heart operations and cancer treatment, or alternative therapies such as stem cell treatment unavailable at home."

And that's already occurring. As folks begin to see hospital waits getting longer and longer, and the costs of care getting higher and higher, it doesn't seem far-fetched that those who can will opt for a short (or long) plane ride, the expenses of which are potentially more than offset by the savings (and, of course, the actual delivery of care).

Pipe dream much, Henry?

Perhaps, but then again:

"Some US businesses already persuade employees to travel for treatment. Medical tourism experts see that becoming more common in the future. With incentives like deductible waivers, the plan saves money for the insurance company, the business and the employee."

And there's nothing preventing carriers from offering optional med-tourism riders or supplements. And competition among foreign providers for American patients may also prove enticing.

Time will tell.

ADDENDUM: Can't believe I missed something so obvious, but of course the Independent Payment Advisory Board (IPAB) Death Panels will also be a major driver of MedTourism. After all, if you or your loved one (or ones) face a literal death sentence, then a quick jaunt to (say) Costa Rica may seem pretty reasonable.

Tuesday, November 06, 2012

Speaking of pains in the...

Although the new ObamaTax rules require health insurance policies to pay for routine colonoscopies (YMMV), that may turn out to be not much of a big deal:

"For some people, one colonoscopy at age 50 may be enough for their whole lives, a new study suggests."

The study found that folks who got a "clean bill" from their first procedure turned out to live just as long as those who repeated the process a few more times. Which isn't to say that no further effort's required:

"[F]or people who received a negative result on their first colonoscopy, it is reasonable to switch to other, less invasive methods for subsequent screenings."

Whew!

Monday, November 05, 2012

Ca$h for (Annuity) Clunkers

Fortunately, this isn't a government-run program:

"Hartford Financial Services Group Inc. has offered some of its annuity clients cash for their contracts."

As regular readers know, Variable Annuities can be solid financial vehicles (they can also be dangerous, but that's another post). When the stock market takes a dive, insurers who issued the policies can find themselves "upside down" because of guaranteed payouts in the contract.

So Hartford's looking to get out ahead of the problem by buying out policyholders who themselves might be feeling a financial pinch. So if you're a Hartford Variable Annuity owner, best be watching your mailbox.

Shecantbeserious keeps flailing away

Mme Secretary just can't seem to help herself:

"The Obama administration is relying heavily on outside contractors to implement a core component of [the ObamaTax[ as it races to set up a federal health insurance marketplace before 2014."

When you have to pass it to learn what's in it, hilarity ensues.

And by "hilarity," I mean "incompetence:" in the rush to set up phony Exchanges, Ms Shecantbeserious has continued to spread her largesse to her cronies, including a subsidiary of United Healthcare.

But wait, weren't we told that private insurance companies were evil, and at the root of all of our health care problems? Apparently that hasn't fazed the Secretary, who's contracted with Quality Software Services, Inc. (QSSI) to build and maintain the databases that will form the backbone of the Exchanges.

All of this took place, of course, with no oversight or input from the Securities and Exchange Commission, which would seem to be an indication that all is not aboveboard. But of course, this hasn't stopped Ms Shecantbeserious before.

After all, what could go wrong?

[Hat Tip: Hot Air]

Obamacare to create Millions more working poor

Obamacare penalizes employers for full-time (FT) employees that are not insured if they don't offer affordable and essential coverage. Employers will obviously look for ways to minimize this damage. One way is by turning FT workers into part-time (PT) employees.

http://nrn.com/article/restaurants-mitigate-health-care-costs-cutting-hours

Darden Restaurants runs over 2000 restaurants, they are testing working employees 29 hours. I have heard of nursing homes in OH that are also moving their FT to PT.

You would think this is a problem for employees, having their hours cut, are they going to have to find second jobs? Turns out it might be win win for everyone but the taxpayors.

Someone working full time making $9.50 per hour makes $1646.92. If they have their hours cut to 5 3/4 a day they would make $1,183.72, a pay cut of $463.20...or is it.

With two people in the household working full time they do not qualify for Food Stamps. Working 2.25 hours less they qualify for $367 a month in benefits. 

Once you qualify for food stamps you automatically qualify for a free lifeline cell phone, worth about $30 per month. 

They would also now qualify for utility assistance.

Instead of paying 9.5% of their income to be on their company plan they pay 2% under the exchange saving an additional $88.78 per month.

Not counting any other additional programs and assistance, by working fewer hours these employees gain  $485.78 in taxpayor funded benefits to offset $463.20 in lost wages. The employer also avoids any taxes for not offering coverage.

Besides all of the problems Obamacare creates for the insurance industry it is likely to push millions more into poverty with even fewer chances to get out.


Sunday, November 04, 2012

Taxes and Fees and Penalties - Oh my!

FoIB Bob D sends us this report from Aetna enumerating the new taxes on tap for us under the ObamaTax.

Here's a taste:

■ Health Insurer Fee
■ Transitional Reinsurance Program Contribution
■ Patient-Centered Outcomes Research fee
■ High Value Plan tax (aka **BMW** Cadillac Tax)


But wait! There's more!

New annual taxes on "Big Pharma," new annual taxes on medical device manufacturers, and the list goes on.

Download the report here.

Friday, November 02, 2012

E&Oxchanges

Because we already know just how efficient government bureaucracies are (*cough*), the latest anticipated problem with the ObamaTax Exchanges should come as no surprise:

"The [ObamaTax] could create new opportunities for employers to get health insurers to compete for their business -- and new opportunities for health insurance exchanges to mess up enrollment."

Think about it: these are the folks who run the Post Office and the DMV, and they're going to be in charge of making sure that employees are properly enrolled when employers begin to shed group health plans.

This is pure wishful thinking:

"[B]rokers have to think just as hard about how the enrollment process will work when they are placing business through an exchange as when they are dealing with one of the "back end" companies that handles enrollment data or send enrollment data directly to insurers"

Um, no, they're not, because no professional agent is going to touch an Exchange-based product with a 10 foot Czech. And those dumb enough to go that route have bigger problems than Errors and Omissions coverage.

And woe to the employer that thinks going through an Exchange is a good idea:

"An enrollment system may greatly increase the employer's risk ... by letting employees sign up for coverage they are not eligible to buy."

Why would any reasonably intelligent employer even bother? Much more cost effective to delete the group plan and take the (nominal) fine tax hit. After all, choosing to use an Exchange means that the employer is trusting a government bureauweenie to get things right and if they don't, well, good luck holding them accountable.

But hey, it's a Brave New World.

Thursday, November 01, 2012

ObamaTax legal update

Early last month, we noted Liberty University's pending ObamaTax lawsuit challenging the Employer Mandate. Today comes word that the Justice Department apparently has no objections to the lawsuit going forward [ed: I'm not a lawyer - and I didn't stay in a Holiday Inn Express last night - but who cares if the DoJ objects?]:

"In a brief filed with the Supreme Court late Wednesday, the Justice Department said the court should clear the way for a possible new hearing in the lawsuit filed by Liberty University."

It's still a long way from a "done deal" but at least there's progress.

LTCi November

November's been designated as national Long-Term Care Awareness Month. We've blogged on Long-Term Care insurance (LTCi) often here; my favorite post on the subject (and one I send to pretty much every prospective LTCi client) is this one from LTCi guru Herman Bruns.

Another LTCi expert is Christine van Breukelen, who alerts us to these "fun" facts:
■ Most long-term care is received at home; not in a nursing home.  In fact, 43% of long-term care insurance claim benefits paid to individuals covered home care (and only 24% paid for nursing home care.)

■ One of the significant ways to save on long-term care insurance protection is to take advantage of available discounts.  People in good health can save.  You can lock in these savings even when your health changes.  Less than half (44%) of people between 50 and 59 qualify though and that percentage declines at older ages.  Why not see if you qualify.

■ Married couples can save on long-term care insurance, sometimes even when only one person is protected.  And with new "shared care" options, two people can actually share each other's coverage.   Less money … more benefit … worth considering.
And Chris adds: There's a great saying; Failure To Plan is a Plan For Failure.  Your first step should be getting the information you need to protect yourself, your family and your loved ones.

Helpful ObamaTax recap

Amelia at Nerd Wallet has a great post neatly summarizing and explaining key fallacies of the ObamaTax.

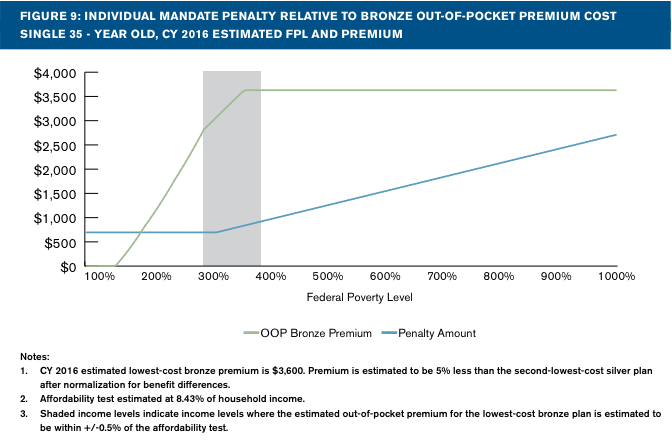
I especially liked this graph, which underscores a point we've been making for a long time (that for most folks, paying the penalty and buying coverage only when it's needed will be the most cost-effective strategy):

[click graph to embiggen]

Do check it out.

Wednesday, October 31, 2012

I was told there'd be no math

So what do these three (seemingly disparate) groups have in common:
■ People in prison
■ People living below the poverty line
■ Illegal immigrants
Give up?

"In just 14 months, Americans will be required to prove that they have federally "qualified" health insurance or face an [ObamaTax] of $695 to $2,085"

Well, most Americans. The folks comprising the three groups listed above are exempt (Sorry, Mags). And when taken as a whole, they represent over 16% of the people who live here.

They have something else in common, as well: they're the folks who, directly or indirectly, gave us the ObamaTax.

How's that, Henry?

It's pretty simple, really: the #1 selling point of the train-wreck was that some 15% or so of us were uninsured for health care. Folks in jail have no need of insurance, since their care's on us. The poor already had a myriad of social safety nets in place (eg Medicaid, SCHIP, etc). And illegals get de facto free health care.

Take out these three groups, and you're left with a handful of Americans who were uninsured (and/or uninsurable), a problem easily fixed without upending 1/5 of our economy and forcing us into nationalized health care.

Gee, thanks bunches.

Cavalcade of Risk #169: Up & Running!

Ray at the Excess Return blog makes his CavRisk hosting debut with this edition, chock full of interesting posts and helpful recaps.

Well, at least it’s free…

A report from the Physician’s Foundation lays out a very grim picture of the future of medicine in America.


This paragraph sums up medicine today:

“PRACTICE EROSION
Over the last half century or more, medicine has evolved from the province of solo and small group practitioners who contracted directly with patients, to an increasingly centralized profession in which treatment is paid for by third parties. Several decades ago, both Medicare and private insurance companies paid physicians retroactively for “usual, customary and reasonable charges,” meaning doctors typically received what they invoiced. This system has been repeatedly modified since, in an effort to reduce costs and manage care, often creating a disconnect between the services physicians provide or believe is appropriate and the services for which they are compensated. This trend may reach a culmination on January 1, 2013, when physicians are due for a 30 percent reduction of their Medicare reimbursement under Medicare’s Sustainable Growth Rate (SGR) formula.”

So physicians today are paid what the government says they should be paid.  The only option for a physician is to become non-participating with all insurance companies, concierge, or direct care, all of which are all cash paid basis for the patient.  This directly impacts a patient, as individuals are becoming more responsible for rising insurance premiums in conjunction with physicians moving away from the third party payment system.

Additionally, “the bar to professional entry for physicians keeps rising, with four years of college education, four years of medical school, and as many as seven years of residency training necessary for those who wish to sub-specialize. Medical education and training come at a high cost, as medical school graduates now carry an average of $156,456 in educational debt, according to the Association of American Medical Colleges (AAMC).”

“FLAGGING MORALE, PERVASIVE PESSIMISM
When asked which best describes their feelings about the current state of the medical profession, only 3.9 percent of physicians used the words “very positive,” while 23.4 percent of physicians indicated their feelings are “very negative.” The majority of physicians – 68.2 percent -- described their feelings as either “somewhat negative” or “very negative,” while only 31.8 percent of physicians described their feelings as “somewhat positive” or “very positive.”

“The great majority of physicians (84.2 percent) agree with that the medical profession is in decline…. Practice owners are more inclined to believe the medical profession is in decline than are employed physicians and specialists are more inclined to believe the medical profession is in decline than are primary care physicians.”

This attitude is pervasive in the medical community.  Physicians are working harder to make the same amount of money they made a decade ago.  Regulations are sapping physicians' time in unnecessary paperwork.

“There is no disputing that medicine is one of the most highly regulated of all professions, and that physicians must adhere to a vast array of laws and requirements imposed by the government and third party payers…. The Medicare regulatory code stipulating provisions by which physicians must abide is over 130,000 pages long.”

Costs such as EMR’s and staff are eating into an already thin profit margin.  Combined, these stressers are reflected in the survey in these findings:

“Over one third of physicians would not choose medicine if they had their careers to do over.”

“Over 60 percent of physicians would retire today if they had the means.”

“In the next one to three years, over 50 percent of physicians plan to cut back on patients, work part-time, switch to concierge medicine, retire or take other steps that would reduce patient access to their services.”

The exodus of doctors from the practice of medicine has begun and the nations brightest and best are no longer interested in a career in medicine.  The high caliber of medicine in America, which was developed through the free market of capitalism, has been brought to the level of mediocrity.  Well, at least it will be free.

More on that 3000% ObamaTax insurance rate decrease [UPDATED]

Not. Happenin'.

From United Health One (formerly Golden Rule) email:
"We will no longer provide our initial 12-month rate guarantee for plans with January 1, 2013 or later effective dates to allow for required changes resulting from the [ObamaTax]."
Ooops.

UPDATE: And the Cato Institute's Michael Cannon reports that the Golden State will see its citizens' insurance premiums shoot up some 25% as a result of the ObamaTax Exchange scheme:

"Under a new rating map approved by state lawmakers, the Department of lnsurance estimated that premiums for similar coverage could increase as much as 25% in West Los Angeles, 22% in the Sacramento area and nearly 13% in Orange County."

Ooops, indeed.

HWR under the 'scope

Tuesday, October 30, 2012

Bad News for Buckeyes

The ObamaTax is gonna hit us in the wallet, and the waiting room:

"A non-partisan study found that, by 2017, individual premiums in Ohio will increase by as much as 85 percent. In addition, Obamacare will deeply cut Medicare Advantage for more than 700,000 Ohio seniors enrolled in the program. And more than 30 percent of Ohio physicians say that they will place new or additional limits on accepting Medicare patients."

We've already seen major rate increases, although it's not fair to lay the blame entirely on the ObamaTax. Health care costs drive health insurance costs, and these are influenced in part by utilization and medical inflation. Still, it's undeniable that at least a chunk of these increases can be laid at the feet of the train-wreck.

Medicare Advantage plans, which actually help rein in some health care costs and offer our seniors choice in health care, have been on the proverbial chopping block for a while; it's no surprise that the ObamaTax will decimate that market.

And of course regular IB readers have known about the coming provider shortage for a while now.

[Hat Tip: Bob Vineyard]

And now for something completely different...

If you are interested in the relationship of science, religion and current events, you might want to check out a new blog by a good friend (and mentor) of mine, Dr Stuart Fickler.

Called the "Secular Kabbalist," Stuart has a Ph.D.in theoretical physics, and "is dedicated to exploring the complementary relationship between religion and science, and its impact on the realities of today."

From one of his most recent posts:
"Humanity has lived under an illusion.  Many believe that we have unlimited independence of choice.  Reality demonstrates otherwise ... The universe is a system.  Everything in it is connected by fields, such as gravity, electromagnetism, etc.  Nothing changes in the universe without the entire universe being affected."
Heady stuff, to be sure, but quite accessible. Recommended.

This Sceptered Isle - Part CLXXXIV [UPDATED]

"Caroline Cassin, 29, who suffers from Cystic Fibrosis (CF) has been offered a new drug free of charge for a limited period by the makers but her NHS hospital is refusing."
Why would that be?

One must read to the very end of the article  to find out.
"The trust decided not to obtain Kalydeco on a compassionate basis because the drug company scheme is temporary and the trust would face withdrawing the medication when the scheme stops."
So is the issue how best to provide life-preserving patient care?  Is the issue how to save money for the NHS hospital trust?  Is the issue how to protect the hospital trust from political fallout?

Whatever the answers, I think this is how so-called "death panels" work in real life.  They don't march in and command "off with your head".  Instead, they work quietly, in private; they employ trusted physicians and other medical professionals under the authority of government who decide whether to block certain types of medical care from certain patients.  This saves money without the ugly and potentially distasteful public task of later having to withdraw that medical care from the unfortunate patients.  

Innocuous . . . really.  And fair.  Right?

UPDATE [We get results!]:

"Medical Director for Heart of England NHS Foundation Trust, said: “Since our last statement we have continued discussions with the company Vertex who produce the drug Kalydeco.
 Following these discussions, we are very pleased to announce that they have taken the decision to offer the treatment on a compassionate basis to named patients, without limiting the offer to a fixed period of time."
Removing the time limit means the hospital (Trust) will not face public calumny on account of withdrawing the treatment at the end of some fixed treatment period.

Ironic, isn't it, that public calumny was necessary to move the hospital trust - and the drug maker - to this decision?

Also worth noting that public opinion still counts for something - even in a quasi-socialist nation like UK.

Not What it Seems

Bob posted about a woman who was charged for “asking too many questions.”  The article in question is about a woman, Susan Krantz, a registered nurse who was confused by her bill. The article's title - "Questions can trigger split charge" - is misleading, as no one is charged for asking too many questions.  What happened in her case is that she went in for a wellness visit and then asked the doctor about a problem, a sore hip.  At that point the visit went from a regular wellness visit to a sick visit or as the article points out, “an “acute care” matter.”

By current policy, there is no charge, referred to as co-pay or out of pocket expense, on an annual wellness visit.  What is misunderstood is that once a person brings up an acute care issue, such as an injury or illness, or if in the course of the exam the physician discovers an acute care issue, such as a lump or other malady, and then the appointment becomes a sick visit and is billed accordingly.  This billing is subjected to a deductible and co pay, which is the patient’s responsibility.  CMS defines a wellness visit as:

As of 2012, the annual wellness visit benefit includes the following services:

■ Routine measurements, such as your height, weight, blood pressure, and body mass index (BMI);
■ Review of your individual medical and family history;
■ Review of the medications, supplements, and vitamins that you are currently taking;
■ Discussion of the care you are currently receiving from other health care providers;

■ Review of your functional ability and level of safety (for example, your risk of falling at home), including any cognitive impairment, as well as a screening for depression;
■ Discussion of personalized health advice that takes into account your risk factors and specific health conditions or needs, including weight loss, physical activity, smoking cessation, fall prevention, and nutrition;

■ Discussion of referrals to other appropriate health education or preventive counseling services that may help you minimize or treat potential health risks;

This list does not include care for acute problems, such as the sore hip brought up by Ms. Krantz.

The article states, “In a written statement, the medical provider said that “the insurance company may require that patients pay or make a co-pay for services beyond the ‘preventive’ part of the appointment.”  The moral of this story is that in the end the patient is responsible for the consequences of any medical appointment with a medical provider, so be prepared.

Monday, October 29, 2012

Yikes! Obamacare Is Even More Unpopular Now than in 2010 [UPDATED]

"Americans support [PPACA] repeal by an even wider margin than they did in the immediate aftermath of its highly unpopular passage ... by a margin of 15 percentage points (54 to 39 percent), likely voters now support the repeal of President Obama’s centerpiece legislation.  In the first three polls taken in the wake of the House’s passage of Obamacare (on March 21, 2010), Rasmussen showed that likely voters then favored repeal by margins of 13 points (55 to 42 percent), 12 points (54 to 42 percent), and 12 points (54 to 42 percent)"

I seem to recall a time when the political leadership claimed that they had to pass PPACA so that we can find out what is in it. 

We are finding out.  The apparent result is this steadily growing opposition.  

Fail. BIG fail.

UPDATE [From HGS]: To get an idea why this plan is so hated, here's a link to an interactive timeline of its implementation. Notice that the plan we had to "pass to learn what's in it" comprises over 50 "checkpoints," from Adoption Assistance to taxes on "Mercedes" "Cadillac" plans.

The "Public Option" Lives

It's that time of year when the airwaves are flooded with zombies and other assorted monsters. So it should come as no surprise that the long-thought-dead Public Option has been given new life under the ObamaTax:

"The [Obamastration] will soon take on a new role as the sponsor of at least two nationwide health insurance plans to be operated under contract with the federal government and offered to consumers in every state."

After all, who needs an Exchange when we can just cut out the middleman and go directly ro government-run health insurance? These plans will "compete" with commercial insurers, but it's not exactly a level playing field: how can private companies compete with the Federal leviathan?

The simple answer is: they can't.

It's an expansion of the Federal Employees' health plan, which has worked so well in reining in health care and insurance costs. Since these plans will be subject to regs from at least three different agencies, good luck resolving claims or other issues. Which then brings us to the role of the National Association of Insurance Commissioners (NAIC). That august body "expressed alarm at the prospect of a double standard." I'm sure the Feds will get right on that.

It's interesting timing, as well, since President Obama has decided to discontinue vital health care services for our veterans. Is there a message in this?

Methinks you already know the answer to that.

Saturday, October 27, 2012

Sandy App

For those in the path of Hurricane/TS Sandy (and/or for those who may face other severe weather conditions) the Insurance Information Institute has a cool - and helpful! - app for disaster preparedness. From email:

"The I.I.I.’s “Know Your Plan” app for iPhone provides users with a library of preloaded checklists to guide them through important property protection and preparedness steps. These include specific lists to help prepare for hurricanes, floods and winter weather—the very conditions threatened by Hurricane Sandy, which may turn into a hybrid “perfect storm” with high wind, heavy rain, extreme tides and maybe snow."

You can download the app from iTunes.

Friday, October 26, 2012

Let's play Guess Who?

OK sports fans, here are three paragraphs from an interview with a brilliant and well-known college professor.

I’m quoting these paragraphs here only because in the course of the interview - which is mostly focused on other things - the conversation eventually comes around to ObamaCare.  And then the professor really lets loose.

Aside from the interesting points made about ObamaCare, my question is:  based on the following three paragraphs, can you name the professor?

“. . . Obamacare: of course, we need health care reform in this country. What a mess! Everyone agrees about that. But the Obamacare is, to me, a Stalinist intrusion — okay? — into American culture.”

“You don't want government agencies being empowered to intrude into people's lives like this. The controlling force in Obamacare is the IRS! Okay? This flies in the face of what the Free Speech Movement was about at Berkeley or about any of the values, I feel, of my generation.”

“I don't see progressives. All I see is white upper-middle-class liberals who speak in this unctuous way about the needs of the poor.  They have no connection whatever with the working class. Okay? It's the professional class gone amok. And that's why they don't notice what a bureaucratic nightmare Obamacare is.“

Here is the source.  I think many readers will be surprised.

(The ObamaCare remarks begin at 12:38)

Show me the [Pounds Sterling]

My first reaction on reading the following was disbelief at the incredible cynicism inherent in the Much Vaunted National Health System©. But then I recalled this and it began to make sense:

"Hospitals are paid millions to hit targets for the number of patients who die on the Liverpool Care Pathway ... In some cases, hospitals have been set targets that between a third and two thirds of all the deaths should be on the [Pathway]"

Yes, you read that correctly: the MVNHS© has actually begun (continued?) to set death quotas. When one considers the ObamaTax Independent Payment Advisory Board Death Panel, it doesn't seem like much of a stretch to see this idea taking hold here.

The rationale, of course, is that killing patients denying treatment is an efficient cost-savings measure. Turns out, though, not so much:

"At least £30million [about half a million dollars] in extra money from taxpayers is estimated to have been handed to hospitals over the past three years"

That's quite an incentive to shunt folks off the care line, no? And recall that "[m]edicine has always been more of an art than a science," and it becomes increasingly clear just how easy - and profitable - it becomes to just pull the plug.

Fortunately, only a very few folks end up on there, right?

Sorry:

"LCP is thought to be used in more than 100,000 cases a year"

Ouch.

Health Wonk Review: Pre-election edition(s)

Maggie Maher hosts an unwieldy and, ultimately, unsatisfying HWR this week. As a long-time participant and supporter, I feel obligated to link to it but I cannot recommend clicking through.

My understanding of, and experience with, hosting an edition of the Health Wonk Review is that one chooses which posts to include, along with a (brief) description. Sometimes, a snide or supportive remark by the host is warranted, but Maggie gives vent to full blown diatribes about several of the entries. I find this disconcerting and, frankly, off-putting.

Intriguing Carrier Idea

We've written before about Critical Illness (CI) policies. These plans pay one a lump sum upon diagnosis of a specific major illness or other similar kind of medical issue (transplants, permanent paralysis, that kind of thing). They're relatively inexpensive, and can provide a much needed transfusion of cash, especially if one has a high deductible plan (such as an HSA).

Humana's taking this a step further, bundling their CI plan with their group HSA products:

"[E]mployees receive a benefit after a serious illness, condition, or accident. During their recovery, they and their loved ones can rest a little easier knowing they won’t have to rely solely on their savings accounts or take on additional debt to cover day-to-day living expenses." [ed: from email, so no link]

Pretty clever (keeping in mind, of course, that the ObamaTax wipes out HSA's in the near future).

[Hat Tip: Cornerstone]

Cavalcade of Risk #169: Call for submissions

Ray at Excess Return hosts next week's Cavalcade of Risk - Entries are due by Monday (the 29th).

To submit your risk-related post, just click here to email it.

You'll need to provide:

■ Your post's url and title
■ Your blog's url and name
■ Your name and email
■ A (brief) summary of the post

PLEASE remember: ONLY posts that relate to risk (not personal finance tips and the like). And please only submit if you are willing to link back to the carnival if your submission is accepted.

Thanks!

Thursday, October 25, 2012

Is Medicine an Art or a Science?

My oldest daughter was born with several health issues; a cleft palate, low muscle tone, windswept feet, and jaundice.  As new parents, my husband and I were beside ourselves on how to care for our new baby.  We were lucky to find a pediatrician who calmed our fears while offering great care to our daughter.  A piece of advice that he gave me is that he trusts a mother’s intuition regarding her children; in other words, if a mother thinks something is wrong with her child, she is usually right.  I have used that philosophy for the past 23 years in raising our daughter and two other children and it has always proven accurate. 
Doctor’s use experience as well as education to treat patients.  Medicine has always been more of an art than a science.  Today, however, there is a push to make medicine a science, removing all subjective processes from t he experience.  It is a push under the title of “Medical Necessity”.  Medical Necessity has been pushed by the government for the past few years to have doctors use tests and past performances to treat a person.  Now private insurers are jumping on the bandwagon.  United Healthcare recently released a notice that it would implement Medical Necessity in inpatient care beginning Oct. 1:

“As a reminder, Medical Necessity is the process for determining benefit coverage and/or provider payment for services, tests or procedures that are medically appropriate and cost-effective for the individual member. The Medical Necessity process is based upon a foundation of evidence-based medicine and:
·  Provides an opportunity to address covered services at the individual level to support enhanced access to quality care for the member.
·  Utilizes generally accepted standards of good medical practice in the medical community.
·  Offers timely communication between health plans, members and providers to allow for prospective, concurrent and retrospective review as well as appeal rights for adverse determinations.

This foundation supports United Healthcare’s overall goals for providing enhanced access to quality care by raising performance standards and reducing variation in medical practice, and health care affordability by implementing a process that promotes efficient delivery of high-quality care in a cost-effective manner.”

What is important to note in this missive is the sentence: “The Medical Necessity process is based upon a foundation of evidence-based medicine.”  Evidence-based medicine is defined as "treatment based on tests, labs and best medical practices for the medical condition."  The problem is that diagnosing based on tests and labs is easy for the obvious conditions, such as a broken arm or an ulcer, but as a doctor once remarked to me “you cannot see pain on an x-ray”.  In other words, not all medical problems can be determined from a test or lab.  There are many anecdotal examples of doctor’s misdiagnosing or missing a serious problem, even with tests.  This was brought to attention recently in an article in the Daily Mail about a woman who died from undiagnosed cervical cancer.

If physicians will now only be paid for evidence based medicine, then many diagnoses that are being paid for today - such as chronic fatigue syndrome, depression, or low muscle tone, which cannot be determined by a test but instead by direct observation and physician expertise - will no longer be viable diagnoses.  At the end of the day, as much science as there is in medicine today, it is an art and art cannot be measured.

Medigap not evil?

When they're not screwing up consumers' life insurance choices, the National Association of Insurance Commissioners (NAIC) does try to do positive things. For example, they have a whole committee that's been working to strengthen support of Medicare supplement plans that limit beneficiaries' out of pocket expenses.

The Senior Issues Task Force [ed: good thing they didn't add "Health" in there] has been trying - thus far unsuccessfully - to communicate that message to HHS Secretary Shecantbeserious. Madame Kathy has "asked the NAIC to think about ways to change the NAIC's Medigap model regulation" to further reduce those out-of-pockets. The problem, of course, is that health care costs what health care costs, so someone is going to get stuck with a big bill.

Care to guess who?