Friday, June 14, 2013

Doctors Behaving Badly

As patients, we have all experienced doctors with a bad bed-side manner: gruff in their discussion with you about your issues, leaving you feeling frustrated and angry after the appointment.  While we have been in a fee-for-service type of payment model, this kind of behavior has been tolerated from both patients and administrators, but as medicine moves to payments based on quality, then bad behavior will no longer be tolerated.  This case from 2011 is used as an example in a recent Kaiser Health News article done in conjunction with the Washington Post:
“At a critical point in a complex abdominal operation, a surgeon was handed a device that didn't work because it had been loaded incorrectly by a surgical technician. Furious that she couldn't use it, the surgeon slammed it down, accidentally breaking the technician's finger. "I felt pushed beyond my limits," recalled the surgeon, who was suspended for two weeks and told to attend an anger management course for doctors.”
Administrators have often had to apologize for bad behavior in physicians - especially surgeons - to both staff and patients:
“For generations, bad behavior by doctors has been explained away as an inevitable product of stress or tacitly accepted by administrators reluctant to take action and risk alienating the medical staff, particularly if the offending doctors generate a lot of revenue.”
Physicians understood that they were in charge; they made the money and if they wanted to behave badly, then they could do so without fear of retribution.

In 2009,  the Joint Commission (the body that accredits hospitals) released new guidelines for addressing disruptive and inappropriate behaviors by medical staff.  The Commission recommends that hospitals develop a zero tolerance for intimidating and/or disruptive behaviors.

Medicine has changed, making such behavior not only unacceptable but reckless.  Medicine is a team effort, mandated by government and a natural occurrence that comes with technology and specialization in the medical field.  If a person has a chronic condition, it is not uncommon to have several physicians involved in the care and treatment of the patient.  As more physicians become involved, then more staff, more facilities and more administrators are also involved. And, of course, more potential for personality conflicts.

Quality initiatives are also becoming more important, as hospitals and other care venues are now required to submit quality outcomes to the federal government not only for the purpose of monitoring care but also designating payments. When a physician mistreats a staff member, that staff member has a recourse through labor law which dictates that employees must work in an environment free from hostility or harassment, which could interfere with their job duties and thus patient outcomes.

Fortunately the days of administrators mollycoddling physicians and telling staff that had been verbally harassed “that is how (s)he is, ignore it and go back to work” are ending.  Once payments are based on quality, these physicians will have to change or risk losing money.

Thursday, June 13, 2013

Hey Young Invincible, Can You Afford $6000?

Last week's Ezra Klein interview with Aaron Smith was a doozy. For those who don't know, Mr. Smith is the co-founder of Young Invincibles. The group works to educate and mobilize (their words, not mine) those between 18-34 years of age. For Ezzie it was the same mantra we always hear: rainbows, pots of gold, unicorns, warm and fuzzies, with a whole lot of "free". The reality is much different. Especially for those who are supposed to spread the wealth health risk and enroll in "affordable" insurance.

Much has been said about the so-called Young Invincibles and whether or not they will purchase insurance. A more glaring concern isn't whether they will purchase or what will be subsidized, but rather whether they can afford the high out-of-pocket maximums. Under PPACA the "catastrophic" plan for those 30 and under is alleged to have a deductible of $6000 (or close to it).

The problem for young invincibles isn't insurance premiums, it is their personal finances. Recently there was a post in the Wall Street Journal that showed:
Young people also are likely to have precarious finances and scant savings socked away for emergencies. When asked if they would be able, in one month, to come up with $2,000 for an unexpected expense such as car repairs, 49% of 18-34-year-old respondents said probably not. 
Further, these same invincibles have less discretionary income. Most don't carry insurance because they can't afford the premiums. Paying $100-$150 for the catastrophic plan isn't in the budget. The $20,000-$40,000 they make per year gets completely consumed by rent, car payment, student loans, groceries, cell phone, cable TV, utilities, and cheap beer.

As we approach the deadline of where we are going to force people to buy insurance the biggest question that will remain is: If I have a choice between paying a 1% tax on income OR 3% (minimum) of my income on premiums PLUS a huge out of pocket cost factor should I get sick which one will I choose?

I think you see which way this train is headed.

Just a Minute (Clinic)!

Hard to believe, but we first started covering the "Minute Clinic" phenomenon in the fall of 2005:

"In a little strip mall in San Mateo, California, nestled “between a UPS store and a hair salon” is a new type of doctor’s office ... The office itself is as much coffee shop as medical center: prices for various services and procedures are prominently displayed above a reception desk"

Technically, that story was about QwikHealth, a Minute Clinic fore-runner. But the basic idea was the same: easy access to affordable basic care. We revisited the concept in 2008, when these little beauties started showing up inside Massachusetts "pharmacies and other retailers."

Now, of course, they're ubiquitous, which is both a blessing and a curse: more providers helps meet the increased demand for health care, but it also cuts into more traditional providers' cash-flow. And there's this: "in-store clinics could actually raise overall costs if, by making medical care easier to access, it increased the overall use of services."

Who says more is better?

Actually, it still may be, but then we also need to consider quality of care; that is, is "Dr Nurse" qualified to diagnose and treat what ails ya? It seems safe to presume that for many (most?) common ailments, the answer's probably yes. And for many folks, it may mean the difference between affordable health care and none at all (I'll leave it to the reader to decide if this is a false choice).

[Hat Tip: FoIB Holly R]

California Dreamin': How much is too much?

I find this sad:


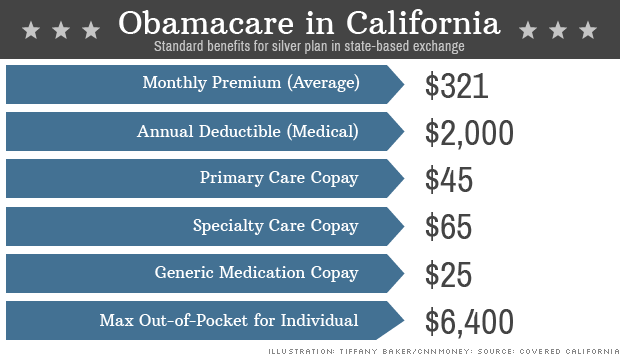
That's a snapshot of how a new ObamaTax "Silver" plan is likely to look (at least in the Golden State). It's sad because it's really no different than how insurance worked before the train-wreck. Too often, individuals focus on the co-pays (for doc visits and meds) without looking at "the big picture." I can't tell you how many times I've presented a High Deductible (HSA) plan only to be asked "what's my co-pay?"

Remember, too, that (for many, perhaps most, folks) any subsidies to which one might be entitled are for the premium which, in this case, represents only about a third of what the total potential out-of-pocket might be. There are few (if any) subsidies for co-pays, deductibles or co-insurance. That's strictly "out-of-wallet."

And even this may vastly understate the problem; as FoIB Jeff M reports, "Kaiser Permanente has offered some of the highest rates in the California health exchanges."

Now why would they do that? The article says that KP itself denies any market-rigging motivation, although it notes that:

"Some experts say Kaiser intentionally bid high to avoid drawing too many customers next year who are sick or who have been uninsured for years and may be costlier to treat."

See, that's just good business sense: we already know that the large majority of folks who actually bother to sign up for (first-time) coverage are those with the most motivation to do so: pent-up needs held back by lack of resources (ie a third party to foot the bill). And who can blame them? On the other hand, had I been the KP spokescritter on this, I would have been sorely tempted to answer the charge with a very simple "d'unh!"

But then, truth often hurts.

Wednesday, June 12, 2013

Some Very Strange Bedfellows


The New York Post reports today (June 12, 2013) that the Freelancers’ Union is seeking relief from Obamacare, and the State of New York may be about to help them.

It seems the Freelancers’ Union – which in 2012 was granted $341 million in Federal loans to set up an insurance CO-OP under Obamacare - has run into a big problem. It’s figured out that Obamacare will seriously damage its insurance business.

Will this damage come from “unexpected” problems encountered by an expert insurance organization blindsided by completely unpredictable insurance requirements?    You can believe that if you like, but I think you would be wrong.

According to the Post, the Freelancers’ Union says that Obamacare’s “onerous regulations and taxes will burden its innovative health insurance model for the self-employed with enormous added costs.”  In other words, Freelancers’ problems are the same Obamacare problems that businesses and other insurance companies have been warning about for the past four years.   They were neither unpredictable nor unexpected.

So what does Freelancers’ want?  It wants authority from the State of New York to convert its health insurance model to a self-funded model.  If it provides self-funded coverage rather than insurance it becomes an issuer of “ERISA Plans” that won’t be subject to Obamacare.

Freelancers’ Union states that Obamacare will cost its members “$38 million a year” which translates into “a per-person premium load of $178 a month”.  That’s the additional amount that would be needed just to pay for the Obamacare load.

Is that devastating?  Well if it is, wouldn't Obamacare be equally devastating to the other insured small group plans in New York – and all across America?

Yet Freelancers’ Union asks the State of New York to step in and spare their successful small-group insurance plan from the devastating effects of the President’s ‘affordable’ health law - but not to spare any OTHER insurance plan from that law.

And say, isn’t it ironic that the Freelancers Union has taken up the conservative cry that Obamacare will hurt more than it can help?  Obamacare is creating some very strange bedfellows.

Remember that 50th employee?

Almost exactly a year ago, we noted the pending demise of 50-employee companies. It now appears that even those fortunate enough to keep their current jobs (let alone obtain new employment) may be subject to reduced hours (and thus pay):

"Under [the ObamaTax], employers' cost to employ workers will climb up to $96.15 per person in the 30th hour they work each week"

That's because of a little-known "feature" of the ObamaTax called "Full Time Equivalent" (FTE). The purpose of FTE's is to discourage employers from hiring too many part-time workers by essentially combining multiple part-timers' hours and calling that one employee. So, for example, an employer with 48 actual full-time employees hires 4 part-timers. The IRS sees not 4 individuals working part time, but 2 working full-time, and that magic 50 employee threshold is reached (thus triggering mandates and fines additional taxes).

But wait, it gets worse (seriously!):

"Employers who offer health coverage that is deemed either too pricey or too skimpy will owe $3,000 for each full-time, 30-hour-per-week, worker who taps ObamaCare subsidies. Because the $3,000 fine is nondeductible, it's equal to $5,000 in deductible wages for a profit-making firm facing a 40% combined federal and state tax rate."

Remember, these are (by definition) small businesses, allegedly the backbone of our economy. Well, they *were* the backbone of our economy.

But wait, it gets murkier:

Co-blogger Bob tipped me to this little gem:

"Under the existing Senate immigration bill, immigrants who have been in the United States illegally can obtain a provisional legal status ... But this population would have to wait at least 13 years to be able to obtain full citizenship, and it isn’t until then that they could qualify for [the ObamaTax benefits]."

The net effect of this little lovely is that employers will have major economic incentives "to hire newly legalized immigrants over American citizens" because the former won't count against them in ObamaTax mandate calculations.

Hooray.

Cavalcade of Risk #185: Lean and (not so) Mean edition

Rebecca Shafer hosts this week's roundup of risk-related blogetry, simple and straightforward, with lots of interesting posts.

Tuesday, June 11, 2013

HSA's vs The ObamaTax: Part XXCVI

As we've previously noted, the survivability of Health Savings Accounts (HSA's)  and High Deductible Health Plans (HDHPs) under the ObamaTax has been questionable. The challenge is that the train-wreck limits one's total out-of-pocket costs and, as important, Exchange-qualified plan designs themselves.

Still, there's no denying the appeal of a plan that offers (potentially) lower premiums coupled with the ability to sock away tax-advantaged dollars to help offset those out-of-pocket costs. While I still have my doubts as to whether these plans will survive unscathed, the folks at Life Health Pro firmly believe that this will be the case:
"Whether your clients fear direct premium increases or higher annual deductibles, their out-of-pocket costs can be slashed using a tax-preferred vehicle that has been on the market for years: the health savings account (HSA) ... For 2013 and 2014, an HDHP is a plan with an annual deductible of not less than $1,250 for self-only coverage or $2,500 for family coverage."
And of course, there may be additional coinsurance that increases one's potential out-of-pocket liability. There are two major obstacles here:

First, Exchange-qualified plans are standardized. That is, there are pre-approved plan designs (often referred to as "metal plans" due to their names - "gold," "silver," etc). I have yet to see one called "aluminum."

Second, plans must meet stringent actuarial value standards, some of which have yet to be finalized. So while I'm hopeful that these plans will, in fact, continue to be available after full ObamaTax implementation, I'm not holding my breath.

Monday, June 10, 2013

IRS - Birth Control - Government Monitoring

To don my tin foil hat for a moment....

The IRS has been in the news for tough grilling of conservative groups seeking tax exempt status, asking for donors, what was discussed, material, etc etc and some claim using that info to target audits.

The IRS is about to start enforcing the birth control mandate.

If you're an agent, any second thoughts on discussing ways to circumvent this regulation or minimize it if your client asks? Sounds crazy, but then so did the idea they would target groups teaching the constitution or speaking up for honest elections. Would you risk being excluded from selling exchange policies? With the new licensing organizations at a national level is it really a jump to think the government might not want to work with agents not working the products they want?

Monday Morning ObamaTax Alert

■ FoIB Holly R alerts us to this breaking news that the ObamaTax will leave some 30 million Americans without health insurance. The whole article is well worth the read.

■ And leave it to Tar Heel State FoIB Jeff M to bring this Buckeye State news to our attention:

"Ohio’s insurance regulators are warning that some health policy premiums may skyrocket next year because of the [ObamaTax] ... The department’s initial analysis of the proposed rates show consumers will have fewer choices and pay much higher premiums for their health insurance starting in 2014.”

But that can't be right: we were assured that premiums would, in fact, fall by over 3000%.

■ Update from Friday's item on renewal dates. We had noted that:

"[A]t least one carrier ... is offering a special, one-time deal to existing client groups to "avoid the effects of adjusted community rating until 12/01/2014"

Since then, we've gotten a bit more detail. What they're offering is the "opportunity" to have two 2013 renewal dates: their original one, and a new 12/1/13 one. The idea is that even though a group would then have two premium increases (despite ObamaTax protestations to the contrary, they're not going down this year) the change would enable them to put off the potentially catastrophic 2014 rate increases.

Interesting gamble.

Friday, June 07, 2013

Friday ObamaTax Miscellany

■ First, a word on "strategery:" Got snail-mail from United Health One (UHC's individual medical outlet), alerting folks that plans "with an effective date up through December 31, 2013 ... can feel secure knowing that their plan/benefits will stay the same until the end of 2014."

The carrier is pretty insistent that plans with 2013 effective dates will see their benefits remain the same until the end of next year. Note, though, that they don't make the same promise about rates.

I have a problem with this: as we noted in April, there's simply no way to know what Ms Shecantbeserious will do with in-force plans.

■ Along similar lines, FoIB Beth D alerts us that at least one carrier (UHC, perhaps not coincidentally) is offering a special, one-time deal to existing client groups to "avoid the effects of adjusted community rating until 12/01/2014"

She helpfully sends along an "Attestation Form" that the group would complete and submit in the next week or so requesting that their effective (renewal) date be changed to December 1rst.

I expect to see similar efforts from other carriers shortly.

■ Finally, The Wall Street Journal finally figures out what we've been saying all along:

"But Chris Angelo, a second-generation owner ... doesn't expect a groundswell of enrollments next year from lower-wage workers ... They'd rather have the cash than pay the employee portion of the premium."

Hunh.

This has ripple effects, of course:

"[E]mployers may struggle to figure out how many of their low-wage workers will opt in for employer coverage in 2014. By the same token, it suggests that many low-wage workers could remain uninsured next year, despite the law's subsidies and penalties."

Where's my free insurance?

Cavalcade of Risk #185: Call for submissions

Rebecca Shafer hosts next week's Cav. Entries are due by Monday (the 10th).

To submit your risk-related post, just click here to email it.

You'll need to provide:

■ Your post's url and title
■ Your blog's url and name
■ Your name and email
■ A (brief) summary of the post

PLEASE remember: ONLY posts that relate to risk (not personal finance tips and the like). And please only submit if you are willing to link back to the carnival if your submission is accepted.

Thursday, June 06, 2013

LICERA (Large Insurance Company Expense Relief Act) out of Committee

Well, technically it's the "National Association of Registered Agents and Brokers Reform Act (of 2013)," but as we noted a few short months ago, its stated purpose and it's actual 'raison d'etre' are quite different.

According to the folks in Capital City, the legislation "before you today represents over a decade worth of effort and ... will finally achieve the goals ... that ensures that regulators can continue to protect consumers"

Lofty words.

Now let's run them through the Capital City Sunshine Removal Filter:

"The NARAB would not only duplicate many (most?) of the functions of the existing NIPR, but it would afford these large carriers a welcome break in their cost of doing business ...  it's industry-funded, which means a non-trivial portion will be borne by smaller, regional carriers to subsidize their larger competitors"

Doesn't have quite the same ring, though, does it?

On the other hand, it does have the value of being, you know, accurate.

Tri-State ObamaTax Roundup

So, news from 3 of the 58 states today.

■ First up, Vermont deals a blow to an ObamaTax co-op:

"A Vermont regulator said today organizers of a proposed Obamacare health insurance co-op who claimed last week they were "blindsided" were told "from the beginning" of problems with their application to operate in the state."

Oops. As we've noted before, co-ops "are nonprofit, customer-owned health plans, designed to compete against the major for-profit insurers." And, as we've also noted, they don't seem likely to fare very well. Screwing up the initial paperwork is probably not a good sign for Green Mountain State co-op wannabes.

■ Next, news from Oklahoma (okay!):

"Oklahoma attorney general Scott Pruitt has found an ingenious way to call a halt to the Obamacare project: Hold the federal government to the letter of that misbegotten law."

Turns out, the Sooner State is sticking by its guns in its federal lawsuit challenging the train-wreck's (sorry, Max!) constitutionality. As one of the 33 states that took a pass on creating its own Exchange, its citizens stand to get hit with tax penalties that seem pretty blatantly illegal.

'Course, they're only illegal if SCOTUS Chief Roberts says they're illegal.

■ Finally, the Natural State (really!) is trying out a bold new Medicaid experiment:

"Arkansas appears poised to move ahead with a plan that will bring private coverage to a population very close to the poverty level while defanging [the ObamaTax's] controversial Medicaid expansion ... that would allow — if the federal government grants a waiver — those for whom the Medicaid expansion was intended to buy private health insurance through the Arkansas health insurance exchange or marketplace."

If you "get" vouchers, then you'll "get" this: instead of an expensive and ineffectual bureaucracy, you give folks the means to purchase their own coverage, which also reinforces the basic (but recently all but extinct) concept of personal responsibility.

Win-win.

Health Wonk Review: I'll Take Health Care for $600, Alex edition

My favorite (health) econ blogger, Jason Shafrin, hosts this week's intriguing round-up of interesting health care policy posts. Don't put yourself in Double Jeopardy, click on over!

Wednesday, June 05, 2013

Who ARE those guys? A bunch of outtacontrol frat boys?

From Buzzfeed via Gateway Pundit:

“IRS confirmed that two employees have been placed on administrative leave — which is paid — and have begun the process of removing them . . . The IRS informed congressional staff investigating the agency that Fred Schindler had been put on leave for accepting the gifts. A second unnamed staffer in the division was also put on leave for accepting the gifts . . ."

So just another case of graft in IRS, right?

Well, not exactly

Schindler is the deputy for Sarah Hall Ingram, who is heading up implementation of the Affordable Care Act for the IRS. Ingram has come under scrutiny recently because she oversaw the division of the IRS which targeted conservative organizations seeking nonprofit status.

Madre de dios

No good answers

Ms Shecantbeserious finds herself once again in the hot seat:

"House Republicans on Tuesday pressed the country’s top health official to cut through the government red tape in order to let a dying child have a chance at getting a lung transplant"

Here's the thing, though: there are no "right" answers here. As much as we like to bust Ms Kathy's chops, I find myself siding with her in this particular instance.

Are you kidding, Henry?

No, and please hear me out.

As we saw in the Nataline Sarkisyan case, sometimes the legacy media is quick to pounce on what appears to be a case of process over life. But is this really the case here?

From the media coverage, it's impossible to know for sure. But the rules have (apparently) been in place since 2005, so it's not exactly news that they exist. And here's the thing: while each life (and especially a child's) is precious, if an exemption is made in this case, how do you tell the next set of parents "no?"

Maybe you don't, but obviously the rule was implemented for a reason. Perhaps we should pause to consider Mr Chesterton's observations on fences.

ObamaTax Scam Alert

As if the actual law itself isn't enough of a headache, clever fraudsters continue to prey on citizens already confused about whether or not they'll be insured. I wrote about one such scam in April, and Patrick had one in May.

Now, FoIB Holly R tips us to the newest iteration:

"USCT [United States Contractors Trust] is targeting people over the Internet with pre-existing health conditions who are experiencing difficulty finding insurance. Desperate to secure individual or family health insurance, the Ohioans eagerly completed contact information forms on innocuous-looking websites"

Unsuspecting Buckeyes provide their contact and bank info, and are told that coverage is in place. The first few claims seem to process fine, but then become ensnared in what USCT says are "computer problems" but which the Ohio Department of Insurance characterizes as a"scam". All the while, premiums (as high as $550 per month) continue to bleed out of the victims' bank accounts.

The Ohio Department of Insurance has "issued a cease and desist order" to the alleged fraudsters; in the meantime, if you (or someone you know) has been targeted, contact the DOI immediately, and direct your bank to stop the auto-withdrawals.

You'll be glad you did.

Tuesday, June 04, 2013

California Dreamin' (a Nightmare?)

Can't win for losin':

"For years, politicians and labor unions have pilloried Wal-Mart and other large employers for paying workers so little that many qualify for government health insurance at taxpayers' expense."

The ObamaTax was supposed to fix that, what with Exchanges and subsidies and (Evil) Employer Mandates and all. So how's that working out for y'all in the Golden State?

Apparently things aren't so, well, sunny:

"Legislators, backed by unions, consumer groups and doctors, are calling for fines that could reach about $6,000 per full-time employee who ends up on Medi-Cal," the state's struggling Medicaid program. Here's the thing, though, Wal-Mart (et al) doesn't pay the tax fine, their customers do. This isn't rocket surgery, it's simple economics.

Sheesh.

Monday, June 03, 2013

Where Is The Outrage? The Compassion? [UPDATED]


"For too long, Americans with pre-existing conditions have been locked out of our health insurance market. Today, the Pre-Existing Condition Insurance Plan gives them a new option -- the same insurance coverage as a healthy individual if they've been uninsured for at least six months because of a medical condition. This program will provide people the help they need as the nation transitions to a more competitive and fair marketplace in 2014."    - HHS Secretary Kathleen Sebelius in 2010

Yes Kathy, the biggest objective for The Patient Protection and Affordable Care Act was to provide access to cost effective health insurance. Back in 2010 we heard the President, HHS, and several members of Congress talk about the benefits uninsured with pre-existing conditions would receive by getting insurance through a high risk pool. This high risk pool would guarantee coverage at an affordable cost. This affordable insurance would become known as the Pre-existing Condition Insurance Plan (PCIP).

PCIP was projected to cover 350,000 people from August 1, 2010 through December 31, 2013. To do so the government set aside $5 billion to cover the projected claims.

Actual enrollment is 135,000 and effective March 2, 2013 HHS has officially "suspended" new enrollment in the program. According to Gary Cohen,  director of the Department of Health and Human Services’ Center for Consumer Information and Insurance Oversight, the program is being suspended due to lack of funds. Cohen said:
"We’re being very careful stewards of the money that has been appropriated to us and we wanted to balance our desire to maximize the number of people who can gain from this program while making sure people who are in the program have coverage...This was the most prudent step for us to take at this point in time.”
Prudent for who?

In addition to cutting off enrollment, those currently enrolled are also facing significant changes. On January 1, 2013 anyone covered under the Federal pool saw their out of pocket maximums increase from $4000 to $6250 per year. Starting in July most of the states who were running their own pools are migrating over to the Federal pool meaning that these folks will also be subject to an increase in the out of pocket maximum. Oh behalf of the many people I have helped enroll in this program I would like to ask the following:

  1. Why in 2011 did HHS decrease premiums for a program that has blown through the projected funding?
  2. Why hasn't HHS or the Obama Administration asked for funding?
  3. Why did the Administration vow to veto a bill that was set to be put forth in the House of Representatives?
Secretary Sebelius and the Obama Administration, if  these are the very people you vowed to help and protect, then why aren't you doing anything about it?

UPDATE [HGS]: And adding insult to injury, FoIB Holly R sends us this:

"Nearly two-thirds of Americans who currently lack health insurance don't know yet if they will purchase that coverage by the Jan. 1 deadline set by the [ObamaTax]"

And worse yet, "less than half of those in the survey ... think they'll get better health care after Obamacare takes full effect. Nearly 50 percent believe the [ObamaTax] will make it more difficult for them to get tests and procedures done in a timely manner"

Sounds like they've been paying attention.

Sunday, June 02, 2013

It's a salad dressing AND a cancer screen!

Okay, this is too cool:

"A simple vinegar test slashed cervical cancer death rates by one-third in a remarkable study of 150,000 women"

You will never guess where - so I'll tell you: "in the slums of India."

In the West, "[p]ap smears and tests for HPV" have saved countless lives, but these are apparently too expensive for poorer nations. Enter vinegar which, when swabbed on the cervix, changes abnormal cells' color, indicating potentially life-threatening cancer.

According the the study, it's "cut the cervical cancer death rate by 31 percent."

Beat that, Honey Mustard!

Friday, May 31, 2013

E(HR)xtravaganza

So the other day, I'm corresponding with the practice manager of one of my physician group clients. This particular PM is extremely professional and knowledgeable, to the point that I rarely hear from her unless I instigate the conversation. I had emailed her regarding the upcoming ObamaTax compliance issue we wrote about earlier this week.

I really just wanted to know if she had any questions, or would like to meet for a mid-year plan review. She politely declined, but what got my attention was her reason: she was knee-deep in implementing new EHR (Electronic Health Record) tech, and that it was proving to be a massive challenge for her - she simply couldn't spare the time for anything else.

This is an obvious problem with such a massive new requirement. But inherent in that challenge is an even greater one: how can smaller practices afford this kind of investment? It is, in fact, one of the most egregious (intended?) consequences of the ObamaTax:

"[F]or those who don’t meet the electronic medical records deadline for implementation, the government has laid out a series of penalties. The message to doctors is clear: implement electronic records or pay a price."

But if you're a small(er) practice, how do you afford this implementation? As Nate pointed out last Fall, "the move to electronic health records may be contributing to billions of dollars in higher costs for Medicare, private insurers and patients ... hospitals that received government incentives to adopt electronic records showed a 47 percent rise in Medicare payments at higher levels from 2006 to 2010"

Which brings me to my real question: doesn't (expensive) EHR implementation actually encourage smaller providers to seek refuge in (ie be bought out by) larger ones? In the long run, economy of scale will always trump the little guy.

Late Morning LinkFest

■ HHS Secretary Shecantbeserious sure loves her slushies. No, not that kind, this kind:

"A little-noticed part of [the ObamaTax] channels some $12.5 billion into a vaguely defined “Prevention and Public Health Fund" ... the department can spend the money as it sees fit and without going through the congressional appropriations process. The sums involved are vast. By 2022, the department will be able to spend $2 billion per year at its sole discretion. In perpetuity."

Well, at least until the money runs out.

■ As we've long documented here at IB, the Much Vaunted National Health System© has become a (sick) joke, and yet the Brits are only now beginning to "get" it:

"The truth is, though, that these problems have been going on for years. The difference now – and the Government deserves credit for this – is that this dirty linen is starting to be washed very publicly"

What's truly frightening, though, is that at one point, the British government allowed a private group to run an MVNHS@ hospital, one which (when under government control) had been "under threat of clsoure due to poor care and financial deficits."

So what happened when a private consortium of doctors took over? Guess.

■ And, finally, some sobering news from FoIB Holly R, who sends us this very helpful, well-balanced NPR story on the travails of long term care, including this moving and informative video:


"48 years old and single"

Who'll take care of Rebecca?

People don't plan to fail, they fail to plan.

Student Health Exchanges

No, not those Exchanges. These Exchanges:

"Students at [University of Illinois Chicago] covered by the school’s health insurance will have an added benefit come the fall: sex change surgery."

We've long dismissed student health plans as poor values, but we never expected this turn of events.

One presumes that Ms Shecantbeserious is eying this development with a gleam in her eye....

Thursday, May 30, 2013

ObamaTax: Another Nail

As we've long documented, one of the (intended?) effects of the ObamaTax is a looming physician shortage. But perhaps some clarification is needed: the shortage is most likely to hit the insured and/or less wealthy demographic first.

Why is that, you ask?

Well:

"Dr. Michael Ciampi [has] ... stopped accepting all forms of health insurance. In early 2013, Ciampi sent a letter to his patients informing them that he would no longer accept any kind of health coverage, both private and government-sponsored"

And to make sure his patients know exactly how that would impact them, he's also taken the full-transparency route (for which we also applaud him) by posting all his prices on-line.

Regular readers may recall our (exclusive) interview with Dr Rob Lamberts last fall, when he explained how his new practice model - Direct Primary Care (DPC) - works:

"The DPC model is one in which the patient pays the doctor directly for their care, usually in the form of a monthly "subscription," plus or minus a fee for visits."

That's different from how Dr Ciampi has evolved his practice; he "collects payment at the end of the visit, freeing him of the time and costs associated with sending bills."

It also frees him to charge whatever he likes (well, whatever the market will bear, anyway) without having to answer to insurance or government bureaucracies. It also means that he can spend more time with patients. Nothing wrong with that.

California's Sneaky Little Trick

There has been much discussion about affordability in the insurance exchanges. From huge potential rate increases to lower than current rates being proposed under Covered California, the range of costs vary significantly.

So it came as a surprise last week when news broke that California's program was showing lower than projected premiums. Ezra Klein called it "Very Good News for Obamacare." Major news networks cited the release telling viewers that premiums were going down.

Then came the rest of the story. Indeed Covered California was going to see a rate reduction for individual insurance. BUT, these plans were compared to the average small group plans. For perspective, the average premium for individual plans sold through EHealthInsurance in California last year was $177 a month. Covered California said the average premium for the three lowest Silver plans statewide was $321 a month, albeit for more comprehensive benefits.

So, why compare 2014 individual rates to today's small group rates? Well, Covered California provided this little gem for you:
"It is difficult to make a direct comparison of low rates to existing premiums in the commercial individual market because in 2014 there will be new benefits and today’s coverage on an actuarial basis is all over the map. The best frame of reference is by looking at current rates available in the small group market in California. Each market is a competitive market with guaranteed issue. Comparing rates to comparable products in the small employer market, rates ranged from two percent above the 2013 average premium to 29 percent below the rates in California’s most populous markets. This is impressive since the 2014 products include doctor visits, prescriptions, hospital stays and more essential benefits."


What's really going to be impressive is if these "preliminary" rates will actually hold.

Wednesday, May 29, 2013

Cavalcade of Risk #184: Post-Memorial Day Risk-a-thon

Jeff Rose hosts this week's small - but powerful! - roundup of risk-related posts. From fast-food to k-rations, you'll run little risk of being disappointed.

Thanks, Jeff!

MVNHS© Back in the News

Thanks to alert IB reader Peter K, we have two new items to add to our Much Vaunted National Health System© database. Last month, we noted that "[MVNHS©] doctors are prematurely ending the lives of thousands of elderly hospital patients because they are difficult to manage or to free up beds;" this was one side of the coin. It only gets worse, though, when one considers the other side of it:

"Patients undergoing planned operations on the NHS are far more likely to die if they have their operations towards the end of the week ... those who had surgery on a Friday were 44 per cent more likely to die following the procedure than those who had the same operations on a Monday." Of course, when you have an overworked and largely unaccountable group of people providing "care," that TGIF mantra becomes somewhat problematic, no?

It gets worse, though. One of the early criticisms of the ObamaTax is that you'd have care providers with the compassion of the DMV. This is already the case under the MVNHS©, and it's the direction we're headed:

"Almost 3,000 people may have died unnecessarily in just one year at the 14 NHS trusts whose excessive mortality rates were reviewed in the wake of the Mid Staffordshire scandal"

Regular readers may recall that we covered that particular shanda over 4 years ago (and it's still making news):

"Appalling standards of care that may have contributed to the deaths of at least 400 patients at a hospital trust were missed repeatedly by managers and regulators ... at Mid Staffordshire NHS Foundation Trust"

At least they've learned their lesson, though, right?

Um, not so much:

"The worst figures were recorded at Blackpool Teaching Hospitals where, in the year to October 2012, the number of deaths anticipated was 1,947 but actually there were 2,357, a difference of 410." [emphasis added]

This is extraordinary, on several levels. First, whatever are they teaching at this hospital? Advanced courses in euthenasia? Second, that "difference of 410" doesn't seem like so much, until one looks at the fact that they were off by almost 30%.

That's not "margin of error," that's Margin of Kevorkian.

Tuesday, May 28, 2013

Tuesday Afternoon LinkFest

■ First up, via email, United Healthcare lets us know that its "Early Warning Report forecasts the states, legal entities and group sizes ... that are currently eligible to be issued MLR premium rebates by [UHC] associated with the 2012 calendar year. Any owed rebates will be paid in July ... There are 21 states and two territories in which UnitedHealthcare does not currently anticipate paying any rebates associated with group business"

Don't spend it all in one place.


■ The Council for Disability Awareness has just released its 2013 Research Report, focusing on the differences between how employees perceive disability benefits versus how HR folks understand them. As one might imagine, it's a rather wide gap:

♦ Most HR professionals (84 percent) believe the ability to earn an income is their employees’ most valuable financial resource, yet only 26% thought their employees were adequately prepared to withstand a disability


♦ HR professionals believe their employees are financially vulnerable to a loss of income

♦ Both HR professionals and their employees severely underestimate the odds of becoming disabled

There's more, including the odds of becoming disabled and for how long. Recommended, and available here.


 ■ Some good news and bad news on the ObamaTax front. First, the bad news (from its proponents' POV): voters favor repeal by a 22-point margin. One supposes that will only increase as we head into Fall, and the (scheduled) Exchange roll-out.

 ■ And now the good news (for ObamaTax opponents): businesses are beginning to "get" just how bad this train-wreck is going to be, and more of them are looking to hop on the self-funded wagon:

"[H]ealth insurers are stepping up. Among their latest offerings: allowing ever-smaller companies to switch to a riskier form of coverage traditionally favored by big employers."

I'm sure Nate would disagree (as do I) with the "riskier" characterization, but the point is, going this route is likely to save some big dollars for employers.

There's a bit of irony here: way back in 2006, we had an exclusive interview with the folks at (now-defunct) ACMG, which was just then rolling out a self-funded program for smaller businesses. Kind of a shame that they were so far ahead of their time, but the post is a good introduction to how these plans work, and why they really aren't all that "risky."

E & Ooops

Much like doctors and lawyers carry malpractice insurance, licensed insurance agents carry Errors and Omissions (E&O) coverage. This type of liability policy protects policyholders (clients) if/when the agent screws up, causing financial loss.

Now come the Navigators. In addition to having to pass no background checks or graduate high school, these folks will also not be required to carry any kind of E&O coverage. Which is actually a good thing (from their perspective) because it's not clear that such coverage would actually be available to them even if they wanted it.

Professional liability insurance (including E&O) requires certain things to be true. In the case of E&O, one must be licensed to sell insurance. Okay, Henry, what about someone who isn't licensed, but needs this kind of coverage, such as an IT professional? There's no Ohio Bureau of Geek Licensing, but these folks would be eligible to purchase
Professional Liability insurance due to training and expertise.

Navigators may be neither licensed nor certified, heck, they don't even need a high school education to qualify; they'll simply attend 20 to 30 hours of instruction and be sent out the door, where they'll spread their, um, "expertise" to unsuspecting victims "clients." But what happens if/when they screw up? What financial recourse will their "clients" have? Their homeowner's policy (if any) won't cover them because it's business, and it's unlikely that they're independently wealthy (deep pockets).

Where's the consumer's protection?

Co-blogger Patrick pointed me to this article, which reports that Navigators in the Hawkeye State will be required to purchase surety bonds. The problem is that a surety bond is not the same as professional liability; it essentially covers theft of money.

For example, a Navigator tells a "client" that coverage will definitely be in force the next day. Three days later, the "client" has a heart attack and runs up tens of thousands of dollars in hospital bills, only to find out that coverage was not, in fact, in force. The most that "client" can recover from the Navigator is whatever he paid the Navigator for his services, not the huge hospital bills he now owes.

This would be where professional liability (E&O) insurance would come into play had a licensed agent been involved. From the article, it appears that Iowa Navigators must be licensed, so they may, in fact, be eligible for E&O coverage. But this is not the case in all 58 states; and therein lies the rub. Having spoken with two actual experts in this area, neither could think of a carrier that would write this coverage.

Which is not to say that it couldn't be developed, should the marketplace demand it. The problems inherent in underwriting such a plan, though, seem pretty insurmountable. And how would one price this in a competitive way? It's unlikely that most of the Navigators are going to be clearing $96-large; more likely, this will be another part-time job to help ends meet. So how do they afford even a minimum premium (generally hundreds - if not thousands -  of dollars a year)?

Yeah, that's what I thought, too.

[Huge IB Thanks to P&C Gurus Teresa S and Bill M for helping me noodle through this post]

Monday, May 27, 2013

ObamaTax Compliance heads' up

Received a sample notice that will (when finalized) have to be sent from employers to their employees later this summer. If you're interested, click here to download it. It's 3 pages, and pretty scary.

Scary, Henry?

Well, here's the thing. The employer will need to complete this form, and attest that, for example, his group plan meets the "minimum value standard." That is, that "the plan's share of the total allowed benefit costs covered by the plan is no less than 60 percent of such costs."

One presumes that the carrier will notify employers whether their group does, in fact, meet that criteria, but it's not entirely clear that this will be so for all carriers in all markets.

There's a related issue that so far seems to be flying under the radar: Exchanges and participation requirements. All carriers require that a minimum percentage of eligible employees sign up for coverage. This is to help reduce the chance of adverse selection, where only the least healthy enroll. The term "eligible" is somewhat flexible, but in general it's full-time employees who don't have "valid waivers." A valid waiver might be, for example, coverage through a spouse, or Medicare. Oddly, an individual medical plan does not qualify as a valid waiver, so that employee must be accounted for in the grand total.

So here's a question: if an employee opts off the group plan in favor of a (subsidized) individual plan from his state's Exchange, is that a "valid waiver?" This matters - a lot - because if enough folks opt off the group plan, it's going to go away, whether or not this is what the employer (and the other employees) want.

But remember: if you like your current plan, you can keep your current plan.

Or not.

[Hat Tip: FoIB Beth D]

Friday, May 24, 2013

Outstanding Carrier Trick

As we reported almost 8 years ago, in our exclusive interview with its Medical Director Dr Dexter Campinha-Bacote, Aetna has long been in the forefront of health care transparency.

Now, our good friend David Williams blogs that the carrier has "won an Award of Distinction  for its short videos designed to help members comprehend and use their benefits."

David offers some great reasons why he approves of this development, and singles out Aetna's terrific payment estimator in particular:

Kudos, Aetna!

About that Union Label

Nice to see the legacy media catching up with us:
"[S]ome unions leaders have grown frustrated and angry about what they say are unexpected consequences of the [ObamaTax] ... The problem lies in the unique multiemployer health plans that cover unionized workers ... union plans were already more costly to run than traditional single-employer health plans. The [ObamaTax] has added to that cost"
Gee, who could have seen that coming?

Oh, yeah.

And it's not just the unions, either. A large majority of Americans (56%) believe it would be "[b]etter to go back to previous system" (pre-ObamaTax).

And this is before the Exchanges and (Evil) Mandate kick in.

What could *possibly* go wrong - An Update

Last week, we noted that the IRS was knee-deep into building the enforcement mechanisms for the ObamaTax. But just how deep are they really?


[Click graphic to embiggen]

Hospital Claim of the Day

Received an audit back on behalf of a client. When we can our plans only pay Hospitals their cost plus a 12% profit margin or Medicare plus 20%, which ever is greater. A member went to a new Spine Surgery Center and the bill was $8,300. Medicare + 20% was $620.28. Billed Charges are 1300% increase of Medicare allowable.

Luckily this new facility was out of Network so we don't have a PPO telling us we have to pay inflated prices. Even a 50% discount, top side for this market, would have been over a $4,000 bill.

Cavalcade of Risk #184: Call for submissions

Jeff Rose hosts next week's Cav. Entries are due by Monday (the 27th).

To submit your risk-related post, just click here to email it.

You'll need to provide:

■ Your post's url and title
■ Your blog's url and name
■ Your name and email
■ A (brief) summary of the post

PLEASE remember: ONLY posts that relate to risk (not personal finance tips and the like). And please only submit if you are willing to link back to the carnival if your submission is accepted.

Thursday, May 23, 2013

Obama Skinny Plan Irony

Prior to ObamaCare a few million people had these not-quite-insurance insurance mini med policies. The administration and pro-reform crowd decided people who purchased these plans needed protection from themselves and set out to wipe them away. Some of these forsaken plans had limits only in the tens of thousands. They might only pay a few hundred dollars per day for hospitalization or surgery.The requirement that plans have no limits, annual or lifetime when fully implemented would see these plans die a deserved death.

These helpless souls had much to look forward to under Obamacare, why they would have full comprehensive coverage at an affordable price....

....or not:
"Wonder what a “skinny” or “low-benefit” insurance plan is? The terms may vary, but the basic idea is that policies would cover preventive care, a limited number of doctor visits and perhaps generic drugs. They wouldn’t cover things such as surgery, hospital stays or prenatal care"
Thanks to ObamaCare they now have even fewer benefits then they had before.

Health Wonk Review: Cereally? Edition

Brad Wright offers up a clever, lighthearted and (his word) sardonic take on the Health Wonk Review. From Einstein to Beckham, angels and bell curves, you're sure to find something to amuse, enlighten and/or enrage you.

Kudos, Brad!

Doctor's orders

"ObamaCare is ... demoralizing doctors, distracting providers toward bureaucracy and away from patient care. It is disrupting quality and access, and damaging health."

Says whom?

Says Dr Charles Willey, "CEO of Innovare Health Advocates in St. Louis, a medical group employing five physicians and five nurse practitioners in five offices."

Dr Willey is suing the Feds to try to derail the "train wreck," focusing on the IRS's unique and powerful role in enforcing ObamaTax provisions. He points to government overreach like  the IRS's "attempt to enforce those penalties in states like Missouri" which, like 32 others, opted out of establishing its own state-run Exchange.

Best of luck to you in your efforts, Dr W.

[Hat Tip: FoIB Holly R]

Wednesday, May 22, 2013

The Grease Fire Spreads [UPDATED]

First HHS "suspended" enrollment into PCIP because of insufficient funding. Now comes word that HHS will be cutting payments to providers who treat those in PCIP. From the New York Times:

Under a new policy issued by Kathleen Sebelius, the secretary of health and human services, “health care facilities and providers will get paid less” for providing the same services to patients in the federal program, known as the Pre-Existing Condition Insurance Plan.
The article further stated:
Federal health officials said the alternatives were worse. If the program runs out of money, they said, some sick people will lose access to health care, and others will be unable to pay for the treatments they receive, forcing doctors and hospitals to write off large amounts of “uncompensated care.”  
In a regulation to be published Wednesday in the Federal Register, the administration says that doctors and hospitals must accept the amounts set by the government as “payment in full” for services in the high-risk pool administered by the federal government. 
On a related note, Ms. Shecantbeserious was busy touting the law in Europe. She "characterized the Affordable Care Act as part of a global movement toward better health through government-led reform."

Based on her words, one would guess that Government will need to seek additional funds (taxes?) while also cutting payments for health services (rationing?) Yep. This is our future under Obamacare.

UPDATE [HGS]: And some breaking news this afternoon on the PCIP front:

"Eighteen states have decided to turn their state Pre-existing Condition Insurance Plan (PCIP) programs over to [HHS Secretary Shecantbeserious]."

As Patrick notes above, the reduced payment scheme is going to really hurt prospective providers, and hence any patients that might want to be treated. But let it never be said that Madame Secretary's minions lack a sense of humor:

"These actions will help ensure the program's smooth transition to 2014"

Droll.

On the Oregon ObamaTrail

Well, some good news for Beaver State residents who may be shopping for health insurance this fall. Unlike so many other states, carriers seem to be supportive of Oregon's Exchange:

"The Oregon Insurance Division has posted individual and small-group rate proposals for 2014 ... rate proposals from a total of 16 conventional carriers and two new CO-OP plans for the exchange and non-exchange markets."

Oregon is one of the minority of states that has chosen to implement its own Exchange, rather than rely on Ms Shecantbeserious and her minions to do so on its behalf. Noticeably absent from the list of participating carriers are Blue Cross and United Healthcare, two rather large elephants in the room. They've chosen to cast their lot with the non-Exchange market, instead.

Interesting developments.

Tuesday, May 21, 2013