Friday, September 14, 2012

About Pre-ex

Finally, a breath of fresh air regarding pre-existing conditions:
"The emphasis on pre-existing conditions is aimed at creating the false impression that the only way to cover anyone who might become seriously ill is with ObamaCare’s heavy-handed and government-centric requirements."
Quite so.

In health insurance parlance, a pre-existing condition (or "px") is generally defined as an illness or injury for which medical advice, diagnosis care or treatment was recommended or received in the 6 months or year preceding the proposed effective date. This is, of necessity, a rather broad definition, but the point is that it's not an insurmountable obstacle to coverage.

HIPAA pretty much did away with that problem when dealing with group (employer-based) coverage: once you'd been insured for at least a year, going from group to group (or even individual to group) meant that you'd be covered right away.

The real problem is in the individual market. Those HIPAA provisions didn't apply to individually underwritten plans, and companies could exclude conditions or people from coverage. Until ObamaCare, the options were so-called "HIPAA plans" (one of the very few individual marketplace reforms in that legislation) and state-based high risk pools.

As Bob's noted, the PCIP program was about the only bright spot in ObamaCare, and even that was hobbled by the stupid requirement that one go "bare" for 6 months.

What's needed is a simple, and ultimately fair, system that recognizes the problem, and applies the group rule to the individual market: once you've been insured for a year, you can "jump ship" to a new plan which would have to cover any (disclosed) px.

Regular readers will notice the problem: isn't that, then, "guaranteed issue?" Not necessarily: some carriers have already long since done away with exclusions and riders, making underwriting more of a binary decision. Coverage is either offered (generally with a higher than quoted premium), or not. I can tell you from experience that far more folks are accepted than declined, which brings us back to PCIP: the current iteration requires not just that one has been turned down, but that one has been uninsured for a half a year. How big a deal would it be to simply swap out that requirement with one that waives coverage for the pre-existing condition for the first 6 months of coverage?

Is this a "perfect" solution? Of course not, but it brings the (perceived) problem down to a manageable size. The linked article goes into some detail about how to "smooth out" some of the wrinkles, especially as regards premium subsidies, and is well worth the read.

I should add: The point of the 6-month wait for px (in the PCIP plan) is that it discourages folks who wait until they're sick to actually, you know, buy the insurance. Beats the heck out of a mandate tax penalty fine.

LifeBridge at 10


Today's episode of Life Insurance Awareness Month is pretty cool: the 10th anniversary of MassMutual's LifeBridge program.

Longtime readers may recall our 2006 post celebrating the program's 4th anniversary; the folks at MassMutual reached out to us to bring us up to date as it reaches the decade mark.

We're joined today by Nick Fyntrilakis, Vice President of MassMutual's Community Responsibility department.

InsureBlog: Nick, what can you tell us about the MassMutual Community Responsibility department?

Nick Fyntrilakis: Many carriers have Community Affairs or Relations departments, we chose "Responsibility" to reflect our core values, a commitment to our communities. It just seems more appropriate. We run MassMutual's charitable giving and philanthropic activities - in fact, MassMutual donates over $7 million to these causes, including scholarships, grants and the like. I should point out, though, that this does not include the money we budget for the LifeBridge program, that's over and above.

IB: As we understand the program, LifeBridge provides free life insurance to struggling families. How does it work?

NF: MassMututal issues a $50,000 policy [ed: 10 year term chassis], payable to a trust for the benefit of one's progeny. If tragedy strikes, the funds can be used for tuition, books, even room and board.

Parents must be aged 19 to 42, a permanent, legal US resident with an annual income of no more than $40,000, and must pass underwriting. That last could be a problem for folks with Type I Diabetes or HIV, for example.

The process itself is pretty simple: there's an eligibility form and an application, and some financial info is also required (to confirm eligibility)
. [Full details are available here]

IB:. How many LifeBridge policies has MassMutual issued over the past 10 years? How many LifeBridge claims have been paid?

NF: We've issued about 12,500 policies nationwide, which amounts to about $625 million in life insurance coverage. To date, we've had about 20 or so claims, which represent over a $1 million paid out to those left behind.

IB: Is there anything else you think our readers should know about LifeBridge?

NF: We're very proud to be the only life insurance company that has this kind of program in place, to have developed and implemented this unique way of giving back. It's literally putting our money where our mouth is, putting our principles into action. And we have a website with all the information your readers might need.

Thanks, Nick, for your time, and continued success with this very worthy endeavor.

[Special IB Thanks to Caitlin Bricker for setting this up]

Cavalcade of Risk #166: Call for submissions

Jeff Rose hosts next week's Cavalcade of Risk - Entries are due by Monday (the 17th).

To submit your risk-related post, just click here to email it.

You'll need to provide:

■ Your post's url and title
■ Your blog's url and name
■ Your name and email
■ A (brief) summary of the post

PLEASE remember: ONLY posts that relate to risk (not personal finance tips and the like).

Thanks!

NB: Thanks to these folks, we're all scheduled 'til the end of the year: Russell Hutchinson, Irwin Jacob, Ray at Excess Return, Jay Norris, Emily Holbrook, Becky Shafer and Van Mayhall.

Thursday, September 13, 2012

Shecanbe-unemployed?

"The Office of Special Counsel (OSC) has concluded that Secretary of Health and Human Services Kathleen Sebelius violated the Hatch Act by engaging in political activity during an official appearance at the Human Rights Campaign’s gala in the battleground state of North Carolina this past February."

"The matter now has been referred to President Obama, who has the statutory responsibility to take “appropriate action” in light of the OSC’s finding that Secretary Sebelius violated the Hatch Act. The presumptive penalty for a Hatch Act violation is termination from government employment, which, if challenged, can be reduced to a suspension of no less than 30 days without pay. Notably, a former U.S. attorney was suspended last year for 100 days for a violation that was considerably more nuanced than the violation by Secretary Sebelius."

I wouldn't hold your breath expecting any accountability here, which is a good thing for this blog, that would be a lot of canned jokes that would need replaced if she was fired.

MVNHS© still swirling

As we continue our inexorable march off the ObamaCare cliff, it may be instructive to note how such a plan fares "in the real world:"


Turns out, when the government runs health "care," people die. That's because care is secondary to rules, and docs aren't incented to put patients' needs first:

"[D]octors’ shifts are limited by the European Working Time Directive and they do not want to work anti-social hours."

In fact, the Much Vaunted National Health Service© just killed off over a thousand seniors, which just has to be good for the ol' bottom line. That's due to the fact that some 70% of hospital beds are occupied by "over-65's." Since the US now has over 10,000 citizens a day turning that magic age, the Brits have company in that regard.

Add to that the existing shortage of hospital beds under MVNHS© "management," and one can see where selective thinning of the senior herd may be desireable.

But hey, it's just economics, nothing personal.

How much do YOU know?

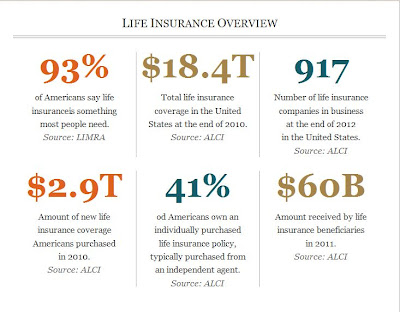
For Life Insurance Awareness Month, the folks at H&R Block (whom Bob quoted the other day as awaiting final IRS rules on ObamaCare) have produced a pretty neat infographic on - of all things - life insurance:

Click image to see a larger versionHow much do you know about Life InsuranceHow Much Do You Know About Life Insurance via H&R Block

Health Wonk Review: Gridiron edition

Louise at Colorado Health Insurance Insider presents this week's collection of wonky posts, all looking to score a touchdown for your attention. here's a LOT of great material here, well worth your time.

Wednesday, September 12, 2012

MVNHS©: Cold and Dead

Fresh off killing young cancer victims, the Much Vaunted National Health Service© continues illustrating the deadly consequences of government-run "health care."

The cold:

"A retired schoolmaster took his own pillows and duvet into a new £170million hospital wing because he was so shocked by the conditions in which his son was being treated."

William Handy (no relation), under treatment for a stomach issue, was found "shivering under blood-stained sheets." When his father complained, he was told that cleaners had "refused to come in because they feared catching an infection."

An infection? At a hospital? Really?

There was also trash on the floor, which the alleged cleaners also refused to handle.

But Mr Handy was the lucky one.

The dead:

"A young mother died from a heart condition after doctors repeatedly told her she only had heartburn when she complained of severe chest pains."

The 28-year old, Gemma Jones, had been seen by various minions of the MVNHS© providers over several months. Each time, she was brushed off, even though a simple (and inexpensive) test could have immediately shown the problem.

Good thing she didn't have to worry about blood-stained sheets, though.

But those are just one-offs, right?

Right?

Not so fast:

"Britain is suffering from an exodus of doctors ... [MVNHS©] is suffering a 'brain drain' of doctors as more medics trained at taxpayers' expense choose to pursue their careers overseas."

And why not? As we've seen above, British medical "facilities" are a disgrace, pay is low, and there's no incentive or reward to excel.

Good thing that can't happen here, though.

Right?

Life Happens

Continuing our coverage of Life Insurance Awareness Month:


Now, you may be wondering what this has to do with life insurance.

The risk of your bikini (unintentionally) coming off is remote.

The chance of dying isn't.

[HatTip: Jon Bloom]

Tuesday, September 11, 2012

Post-Isaac Insurance Tips

The folks at the Insurance Information Institute sent us some helpful information to pass along to our readers. Since this is an area outside our own expertise, I turned to our on-call P&C guru Bill M for vetting. He gave it his seal of approval, so here ya go:

1. Is damage from hurricanes covered under my homeowners insurance policy?

Standard homeowners insurance policies cover damage to the structure of your home and to personal possessions from windstorms such as hurricanes, tropical storms and tornadoes. There is also coverage for storm damage to a garage, deck, gazebo, shed, swimming pool and other structures on your property.

2. Does my renters insurance cover damage from hurricanes?

A renters policy provides coverage for personal belongings damaged by a hurricane. Damage to the apartment’s structure, such as walls and floors, is covered under the insurance policy of the building owner.

3. Are flood losses covered under my homeowners or renters insurance policy?

Flood damage is generally not covered under standard homeowners and renters insurance policies. Flood coverage is available from the National Flood Insurance Program (NFIP) and from a few private insurers. Flood insurance covers losses resulting from heavy or prolonged rain, coastal storm surge and failure of levees or dams ... For more information about flood insurance, watch the I.I.I. video, Water and Flood Damage: What Is Covered and What Is Not.

Introducing: RahmCare!

Earlier this year, Bob noted that, although sound in theory, so-called "workplace wellness programs" aren't really all that effective at reining in health insurance costs:

"Workplace wellness programs sound like a win-win ... Actuarial studies covering thousands of employees over the last 25 years or so don't bear that out"

That hasn't stopped erstwhile presidential advisor (and current Windy City mayor) Rahm Emmanual from implementing his own version:

"Chicago Mayor Rahm Emanuel has announced a new “wellness program” for all city employees and their spouses ... The program, called Chicago Lives Healthy, is technically voluntary; but those refusing to participate in it will be penalized $50 a month"

Gotta love that parsing: it's "voluntary" but refuseniks face a $600 annual penalty tax fine assessment. Unsurprisingly, almost half of those eligible have signed up. The program itself entails an initial biometric screening, a comprehensive written assessment, monthly check-ins with a disease-management company, and the list goes on. It'll be interesting to see how this obtrusion into folks' personal life will ultimately play out, and if the city sees any substantive rate relief as a result.

By the way, I would be remiss if I failed to point out that Hizzoner's brother is the "esteemed" Dr. Ezekiel Emanuel, an outspoken proponent of the "social resource allocation model" of health care.

We know it as "rationing."

Monday, September 10, 2012

Cars and Care (Or: Volts and Valves)

Did you know that General Motors we taxpayers lose almost $50,000 each time a Chevy Volt gets sold?

"[The taxpayer] is taking a $49,000 bath on each Chevy Volt it sells ... the ballyhooed pug-in hybrid vehicles is currently costing upward of $89,000 to produce ... a sticker price of just less than $40,000"

Now, you may be wondering what this has to do with health care.

It's simple, really: the government is (reasonably) good at doing the things for which it was originally intended. But our form of government was never designed to own the means of production - car factories, for example. And because the government is, by definition, the ultimate non-profit, it bring that not-for-profit mindset to everything it touches.

And under ObamaCare, the government essentially owns the means of health care.

Don't you feel better already?

The Best (and Longest) Sentence of the Year


[Hat Tip: Ace of Spades]

Life insurance in 1,000 words (give or take)

Continuing our efforts to promote Life Insurance Awareness Month, here's a nifty "infographic" from Life Insurance Selling magazine:

They also have a very helpful interactive widget featuring easy-to-understand definitions of common (and not-so-common) life insurance terms. Click here for that.

It's not over 'til it's over

In contrast to the brouhaha stirred up by the February 10, 2012 IFR (Interim Final Regulation) mandating contraceptive coverage, the revised IFR released August 15 has received relatively little public attention. (There's a link below to the revised IFR).

The revised IFR says it clarifies that non-church plan sponsors who have a religious objection to the mandatory coverage of contraceptives, may now obtain a one-year deferral of the regulation’s effective date if they meet certain criteria and self-certify their objection. 

The original February 10 IFR exempted church plans from having to cover contraceptive methods, sterilization procedures, and related patient education and counseling.  But the exemption did not apply to church-sponsored colleges, universities, hospitals and other organizations operated in furtherance of the churches' religious missions.  The churches and the church-related organizations objected to the February 10 IFR almost immediately.  The Catholic Church and other churches have sued the administration arguing among other things that the regulation violates the First Amendment.  It’s my understanding those actions are still pending.

The February 10 IFR was implemented August 1st as originally written.  The August 15 IFR states that "In reissuing this bulletin, CMS is not changing the February 10 policy."  While it is a clear abuse of words to call the reissued IFR a "compromise", the administration itself has never called it a compromise but was careful from the very first to call it an “accommodation”. Thus the sole purpose of the August 15 IFR is to add content "clarifying” that plan sponsors who have religious objections - other than churches themselves which are permanently exempted - can defer the effective date of contraceptive coverage in their plans . . . for one year.

The August 15 IFR contains the criteria for obtaining the one-year effective date deferral.  Organizations can obtain the one-year deferral by self-certifying that they meet the criteria.  Naturally, self-certification requires completion of forms, plus distribution of notices to plan members stating that contraceptive coverage will be delayed. 

The IFR as reissued August 15 is here. Additional background here and here and here and here. 

Meanwhile, some Catholic Universities have already begun to cancel their student health plans.

As Yogi Berra once said, “Its not over ‘til it’s over.” (Berra also said “I never said half the things I said.”)

Anyway, this is definitely not over.

Friday, September 07, 2012

SLIRP it up

In honor of Life Insurance Awareness Month, we'll be stepping up our postings on this valuable, but often neglected, coverage. In addition to providing valuable death benefit protection, life insurance can be a useful retirement funding vehicle. FoIB Jeff M explains:

"Using permanent life insurance contracts to supplement a qualified plan is well-established. Called SLIRP, or supplemental life insurance retirement planning, is helpful if one has maxed out on IRA's or other qualified plans.

The "key" to making this work in the manner it's designed is to over-fund a permanent life insurance policy up to the point where one extra dollar paid in premium would make the contract what's known as a Modified Endowment Contract. Typically, this means a Universal Life policy. Another key factor is that it takes about 12-15 years of this maximum funding to realize the level of cash value to ensure long term success.

And, of course, this is a life insurance policy first. Properly structured, the face amount of the policy is kept as low as possible with the maximum amount of premium paid in allowed. And this is where so many of these go awry: failing to properly fund (over-fund) will derail this plan. If/when this happens...the end result hoped for often times isn't realized.

Businesses purchase insurance of this type on their key executives to provide supplemental retirement benefits. Once again, the key for it to be successful is time and money...enough time to fund it properly and funding it to the level needed to generate the income later on. The income comes first in the form of withdrawals and then policy loans.

For business owners looking to start one of these on themselves, I always counsel my clients to make sure that they have the appropriate amount of insurance in-force before taking this additional plunge.

So, is SLIRP right for you? Best to meet with your professional insurance advisor to make sure."

Thanks, Jeff!

Thursday, September 06, 2012

But a lunch break is in our contract

From the Swedish Medical Meatball© files:

"A 72-year-old man having a tumour removed from his kidney died after the chief anesthetist and nurse took a lunch break in the middle of the surgery."

Words fail.

Is this racist?

I really don't know what to make of this (from email):

"Patients’ race and disability status make a significant difference in their compliance with a life-prolonging medication regimen ... Even among individuals with nearly full drug coverage, the difference in adherence rates between racial groups remains" [link to abstract]

They're referring to post-event medication, finding that members of certain groups aren't really keen on follow-through regarding their own health, even if they can afford to.

Here's the problem:

“Physicians should be aware of these differences in adherence as they treat patients”

How?

Just reinforcing the point that one should be taking one's medicine could be construed as racist, with potentially dire consequences to follow. And whatever happened to personal responsibility?

Oh, yeah.

[Hat Tip: UPMC]

ObamaTax News

Almost a half century ago, Supreme Court Justice Potter Stewart observed that "hard-core pornography" was hard to define, but that "I know it when I see it." Now, this post isn't about pornography, but the point holds: how do you define a full-time employee?

If you answered "I'll know one when I see one," you may not be far off:

"Employers can take up to 12 months to determine whether workers are full-time employees for purposes of applying the new federal "play or pay" health benefits rules."

Which becomes an interesting game of chicken with that potential 50th employee.

Regular readers may recall that the so-called "play or pay" rule, aka Employer Mandate, requires companies with 50 or more employees to provide group health insurance. This has the net effect of reducing employment opportunities at a time of record unemployment numbers. Not to mention, what if you're employee #50? How secure are you feeling right now?

Never fear, though, because your boss can apparently take up to a year to decide whether or not you (or your replacement) are worth it.

Don'tcha just love the warm fuzzies?

Wednesday, September 05, 2012

Hey Grandpa, time's a-runnin' out!

This Friday (September 7th) marks the beginning of the end for so-called "Grandfathered" health plans. Regular readers know that we think it's much ado about, well, not much, but it's another sign of the increasing burden of ObamaTax. From a UHC email I just received (notice today's date):

"Grandfather Certification Forms are required for any 1-99 group policies that are in a grandfather position, and must be postmarked no later than Friday, Sept. 7, 2012."

Wow, thanks for the heads' up, guys!